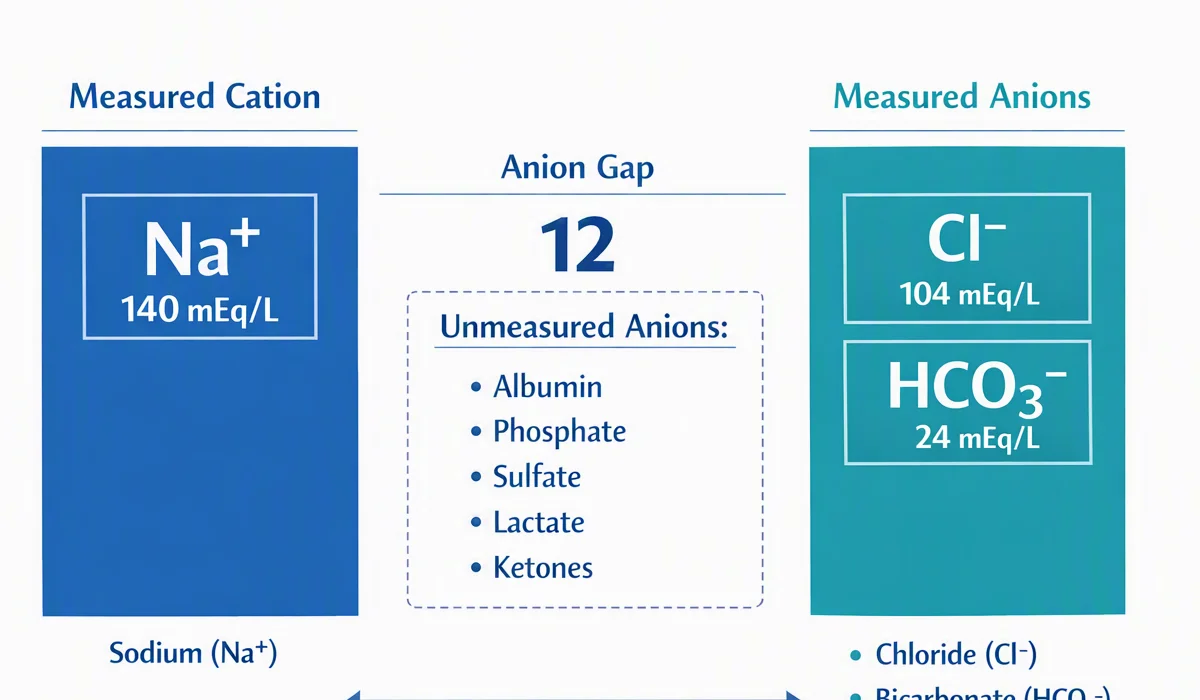
What the Anion Gap Means in Acidemia
The anion gap is a practical way to assess acidemia and limit the likely cause of metabolic acidosis. It represents the disparity between routinely measured serum electrolytes and helps clinicians determine whether unmeasured acids may be present in the blood. In simple terms, the anion gap is a clue about the body’s acid-base balance and whether the problem is being driven by acid accumulation, bicarbonate loss, or another disorder.
Acidemia means the blood pH is below normal. That does not always mean the primary problem is metabolic, but a low pH frequently prompts an acid-base analysis. The anion gap is especially valuable because it can help separate high anion gap metabolic acidosis from normal anion gap metabolic acidosis. That distinction changes the differential diagnosis, the urgency of evaluation, and the type of follow-up testing that may be needed.
At a basic level, the anion gap compares positively charged ions with negatively charged ions in a standard chemistry profile. A higher-than-normal gap suggests extra unmeasured anions, such as lactate or ketones. A normal gap may suggest a bicarbonate loss problem instead. Because of that, the anion gap is not just a number; it is part of the overall interpretation of laboratory values in context with symptoms, severity, and other results.
How to Utilize an Anion Gap Calculator
An Anion Gap Calculator usually uses three primary measurements: serum sodium, serum chloride, and serum bicarbonate. Some calculators additionally allow you to include albumin so the result can be adjusted for low protein levels. This is helpful because the raw value alone may underestimate the true difference when hypoalbuminemia is present.
The usual process is straightforward:
- Enter the sodium value from the chemistry panel. Input the chloride value. Input the bicarbonate value. Examine the calculated anion gap and assess it against the reference range. If albumin is low, calculate the corrected anion gap.
The calculator is most valuable when used for evaluation, not in isolation. For example, a mildly elevated result may be not as alarming if the clinical picture is stable and the patient’s symptoms do not suggest a serious disorder. On the other hand, a markedly elevated value with severe symptoms, abnormal vital signs, or worsening https://anion-gap-calculation.com/calculators/osmolar-gap.html laboratory values needs prompt attention.
Using the calculator also supports more rapid screening for hidden causes of acidosis. A chemistry panel can show the raw numbers, but the calculated difference helps describe the pattern. This makes it easier to decide whether the issue is more consistent with increased acid production, impaired acid excretion, or a bicarbonate-losing process.
Ion Gap Formula and Normal Ranges
The usual anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some laboratories follow slightly different calculations or include potassium, but the sodium-based version is the most widely used in day-to-day practice. Because reporting methods differ, the expected normal anion gap varies with the laboratory method and the local electrolyte panel. For that reason, the correct reference range is the one used by the reporting lab, not a universal number.
In clinical practice, a normal result does not automatically exclude a disorder, and an elevated result does not diagnose a specific cause by itself. The calculation is a clue that must be paired with the rest of the acid-base analysis. A higher-than-expected result suggests an accumulation of unmeasured anions, while a normal result can still be seen in serious illness if bicarbonate loss is being offset by chloride retention.
It also helps to remember that laboratory values may shift during illness or treatment. A changing anion gap can be more informative than a single number, especially when the patient’s condition is evolving. Serial analysis can reveal whether the cause of metabolic acidosis is improving, worsening, or being masked by another process.
Albumin Adjustment and Why It Matters
Albumin is a key unmeasured anion in the blood. When albumin is low, the measured anion gap may seem falsely low even if clinically significant acid accumulation is present. That is why hypoalbuminemia can obscure the true picture and why the corrected anion gap is often preferable than the unadjusted value.
Albumin correction refines acid-base interpretation by accounting for the fact that low albumin decreases the baseline gap. Without correction, a patient with significant acid accumulation might be misclassified as having a normal result. That can postpone recognition of serious disease and undermine the accuracy of the differential diagnosis.
A corrected value is especially useful when the clinical context suggests acidosis but the initial anion gap is not particularly abnormal. In those cases, the raw chemistry may be inaccurate. Correcting for albumin helps return the gap closer to what it would be with normal protein levels, making the analysis more trustworthy.
In practice, the correction is most helpful when evaluating critically ill patients, those with chronic illness, or anyone with low albumin on laboratory testing. It can alter the interpretation from apparently normal to clearly abnormal, which may shift attention toward high-gap causes. The corrected result should still be considered alongside symptoms, other laboratory values, and the full acid-base picture.
Increased Anion Gap Compared to Normal Anion Gap Acidosis
High anion gap metabolic acidosis develops when additional acids elevate the number of unaccounted-for anions in the blood. Common examples include lactate, ketones, and retained organic acids. The gap rises because bicarbonate is consumed buffering those acids, while chloride does not rise enough to keep the gap normal.
Hyperchloremic metabolic acidosis, also called chloride-associated metabolic acidosis, usually occurs when bicarbonate is lost and chloride rises to maintain electroneutrality. The anion gap stays within the expected range even though the patient still has metabolic acidosis. This pattern is important because the underlying cause and treatment vary from those of a high-gap disorder.
Acidosis from lactate is one of the most important high-gap causes because it may indicate poor tissue oxygen delivery, shock, sepsis, medication effects, or other serious illness. The presence of renal failure can also raise the gap because impaired kidney function reduces acid excretion and allows unmeasured acids to accumulate.
Identifying the pattern matters. If the gap is high, the next question is usually what unmeasured acid is responsible. If the gap is normal, the focus shifts to bicarbonate loss, chloride excess, or renal tubular disorders. In both cases, the calculator supports diagnosis by organizing the laboratory picture into a more usable framework.
Common Sources of Acidemia by Anion Gap
Several common disorders can help explain acidemia, and the anion gap assists in classify them into groups.
- Ketoacidosis: Occurring when ketone production rises and acids build up, often with insulin deficiency, starvation, or excessive alcohol use. Salicylate toxicity: May produce complicated acid-base changes and often needs careful interpretation of the entire laboratory pattern. Diarrhea: A frequent cause of bicarbonate loss, usually accompanied by normal anion gap metabolic acidosis. Renal tubular acidosis: A kidney disorder that disrupts acid handling and often leads to a normal gap pattern. Renal failure: Can result in retention of acids and promote high anion gap metabolic acidosis. Lactic acidosis: Often associated with hypoperfusion, infection, medication effects, or severe physiologic stress.
The symptom pattern can also help with interpretation. For example, vomiting, dehydration, infection, altered mental status, rapid breathing, or abdominal symptoms may indicate a specific cause. The calculator does not take the place of clinical judgment, but it can quickly highlight the most likely category of disorder.
In clinical analysis, more than one process may be present. A patient may have both lactic acidosis and diarrhea, or ketoacidosis with renal impairment. That is why the anion gap is best used as part of a broader assessment rather than as a stand-alone answer.
Systematic Interpretation of Acid–base Disorders
When acidemia is suspected, a structured approach is more reliable than looking at one value alone. An arterial blood gas is often used to assess pH and respiratory compensation, while a venous blood gas may also provide useful information in many settings. Together with the chemistry panel, these tests help clarify the disorder.
A useful stepwise approach includes the following:
- Review the pH to confirm acidemia. Review PaCO2 to see whether the respiratory system is compensating or contributing to the problem. Evaluate bicarbonate to determine whether the primary issue is metabolic. Calculate the anion gap from the electrolyte panel. Assess whether the gap is elevated, normal, or corrected for albumin. Apply the pattern to guide the next diagnostic question.
This approach helps distinguish respiratory from metabolic disorders and clarifies whether the abnormality is acute, compensated, or mixed. A low pH with low bicarbonate usually indicates metabolic acidosis, but the PaCO2 helps determine whether respiratory compensation is appropriate. If PaCO2 is higher than expected, a mixed disorder may be present.
The main advantage of this approach is that it links calculation to interpretation. A result that seems small in isolation may still be important if the pH is low and the clinical context suggests a serious cause. Likewise, an elevated gap may need confirmation with repeat testing if the sample quality or timing is uncertain.
When should you to Recheck Laboratory tests or Get Urgent Care
Certain circumstances need rapid reassessment because acid-base problems can worsen quickly. Profound acidemia is especially concerning when it occurs with changes in mental status, trouble breathing, unstable vital signs, or signs of shock. In those cases, immediate medical evaluation is appropriate.
Retesting may be needed when the initial results do not fit the clinical picture, when the patient is deteriorating, or when treatment has begun and response needs to be measured. Rechecking abnormal electrolytes can show whether the bicarbonate, chloride, or sodium values are shifting in the expected direction.
Lactate testing is often important when high-gap acidosis is suspected, especially if there is concern for poor perfusion or infection. Rising lactate can indicate ongoing tissue stress and may signal the need for urgent intervention. Other high-risk results on the lab report, such as extreme potassium abnormalities or very low bicarbonate, also increase risk and should not be ignored.
If the patient has worsening symptoms, confusion, chest pain, rapid breathing, profound weakness, or dehydration, urgent evaluation is warranted. The calculator is useful for initial review and interpretation, but it should never delay care when the clinical presentation is concerning.
FAQ
What is an anion gap calculator used for in acidemia?
Anion Gap Calculator is used to estimate the difference between measured cations and anions, helping identify the likely cause of acidemia. It supports interpretation of metabolic acidosis by showing whether the pattern is more consistent with a high-gap process such as lactate or ketones, or a normal-gap process such as bicarbonate loss.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
The common calculation is sodium minus the sum of chloride and bicarbonate. In other words, anion gap = serum sodium − (serum chloride + serum bicarbonate). The result should then be compared with the lab’s reference range and interpreted in the context of the electrolyte panel and acid-base balance.
Why does the albumin affect the anion gap?
Albumin influences the anion gap because it is a major unmeasured anion in the blood. When albumin is low, the measured gap may be artificially decreased. Albumin correction helps produce a corrected anion gap that more clearly reflects the true acid-base interpretation, especially in hypoalbuminemia.
What does the a high anion gap mean?
A high anion gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and salicylate toxicity. A high result does not identify the cause by itself, but it strongly suggests a high anion gap metabolic acidosis that needs further evaluation.
Can acidemia occur with a normal anion gap?
Absolutely. Acidemia can occur with a normal anion gap when bicarbonate is lost and chloride rises to compensate, such as with diarrhea or renal tubular acidosis. This is called normal anion gap metabolic acidosis, and it is an important pattern because it points to a separate diagnosis and management approach than high-gap acidosis.