What the Anion Gap Measures
The anion gap is a simple way to determine the discrepancy between commonly measured electrolytes in the blood and the unmeasured charged particles that help maintain acid-base balance. In clinical practice, it is most often used to support evaluation of metabolic acidosis and other acid-base disorders.
An anion gap calculator uses standard laboratory values such as sodium, chloride, and bicarbonate to assist in detecting whether there are excess unmeasured anions in the plasma. In routine care, this is a valuable part of clinical interpretation because it can indicate a specific metabolic derangement even before the full picture is known.
The underlying idea is simple: sodium represents most of the measured positive charge, while chloride and bicarbonate represent major measured negative charges. The gap illustrates the relationship between these laboratory values and the unseen ions that are not directly reported on a standard electrolyte panel.
Although the number itself is only one piece of the puzzle, it is a important screening tool for identifying an abnormal acid-base state and guiding a more focused diagnostic algorithm. In settings such as critical care, the anion gap can help triage whether a patient likely has an acid-base disturbance that needs urgent workup.
How to Work with an Anion Gap Calculator
To operate an anion gap calculator, start with a serum chemistry panel and input the input values for sodium, chloride, and bicarbonate. Many calculators also allow entry of serum albumin, which is important when you want an albumin-corrected anion gap.
The calculator calculates the anion gap formula and gives a value that can be compared with the expected reference range. A result above the expected range may suggest excess acids or other unmeasured anions, while a normal value does not fully exclude an acid-base disorder.
For clinical use, the process should be systematic:
- Verify the basic electrolyte values on the serum chemistry panel. Check whether serum albumin is available. Record the input values carefully to avoid transcription mistakes. Assess the calculated anion gap in the context of the patient’s symptoms and other laboratory values. Decide whether an albumin correction is needed before interpreting the result.
The calculator is best used as a supportive aid, not as a standalone diagnosis. A single number does not replace bedside assessment, medication review, or more advanced acid-base analysis. Instead, it helps clinicians identify patterns that warrant a closer look.
Anion Gap Formula and Calculation Methods
The classic anion gap formula is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain laboratories and references include potassium in the calculation:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Both methods are used in clinical practice, but the sodium-only version is more widely used because potassium contributes relatively little to the total. Still, it helps to know which method your calculator uses so you can match the result with the correct reference range.
The corrected anion gap is especially important when serum albumin is low. Because albumin is a major unmeasured anion, low levels can make the uncorrected gap appear falsely normal. In that setting, albumin correction helps reveal hidden acid accumulation that might otherwise be missed.
For practical use, the calculator should explicitly show which method is being applied. That prevents confusion when the result is reviewed alongside other electrolytes and supports more reliable diagnostic support in real-time care.
Expected Anion Gap Range and Meaning
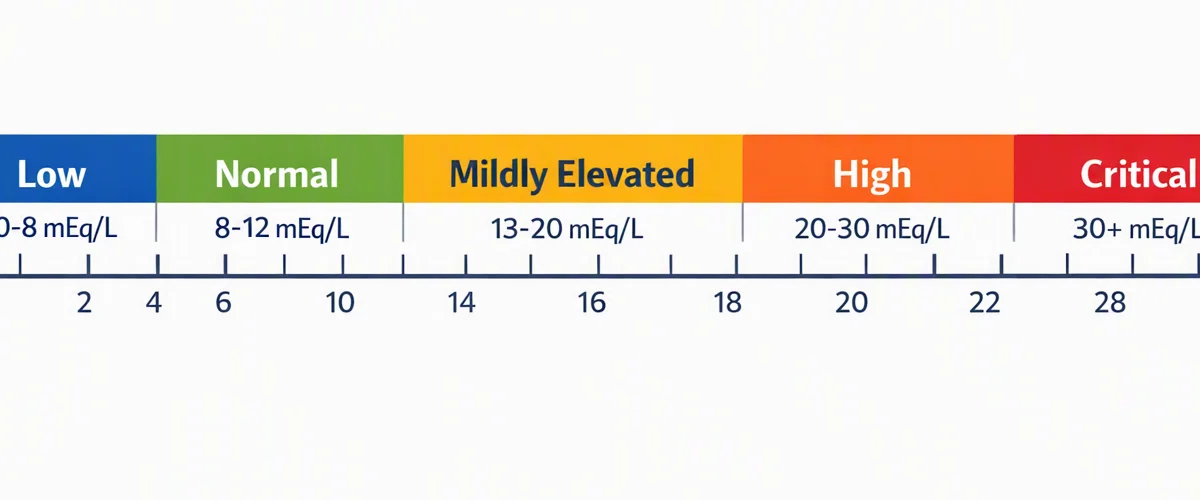
The expected reference range for the result depends on the assay method, testing platform, and whether potassium is included. Because of this, there is not a single standard normal number. Rather, clinicians should interpret the result using the site-specific range reported with the patient’s laboratory values.
A normal anion gap generally suggests that the balance between measured cations and anions is in the normal range, but it does not rule out disease. A patient may still have normal anion gap metabolic acidosis, especially if there is a compensatory rise in chloride.
A high anion gap suggests accumulation of acids or other unmeasured substances. That finding is especially important when evaluating possible metabolic acidosis. However, the degree of elevation may be reduced by hypoalbuminemia or altered by lab variation.
Interpretation should always consider the full clinical picture:
- Is the patient acidemic on blood gas testing? Is there evidence of shock, hypoperfusion, or toxin exposure? Do the electrolytes show concurrent hyperchloremia? Is the bicarbonate reduced in a way that matches the expected pattern?
These prompts turn a raw value into meaningful clinical interpretation.
Reasons of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis develops when acids collect at a faster rate than the body can eliminate them or balance them. This results in a elevation in unmeasured acid anions and a fall in serum bicarbonate.
Common causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, poor oxygen delivery or mitochondrial dysfunction leads to lactate accumulation. In ketoacidosis, ketone bodies build up in states such as diabetic decompensation, starvation, or alcohol-related metabolic stress. In renal failure, the kidneys cannot remove acid effectively, so retained organic acids increase the anion gap.
Additional causes can include toxic ingestions, but the most clinically common scenarios are those above. The practical value of the calculator is that it alerts clinicians to a pattern that suggests a metabolic derangement even before all confirmatory testing is complete.
In clinical assessment, a high result should prompt a search for the underlying driver rather than a focus on the number alone. The next step is to identify whether the elevation is due to hypoperfusion, insulin deficiency, kidney dysfunction, or another process affecting acid-base balance.
Reasons for Normal Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis can also be called hyperchloremic acidosis. In this condition, bicarbonate is reduced or exhausted, and chloride climbs to keep electrical balance. As a result, there is a reduced serum bicarbonate with a relatively unchanged gap.
A common cause is diarrhea, which causes direct digestive bicarbonate loss. Another important cause is renal tubular acidosis, where the kidneys cannot properly acidify the urine or reabsorb bicarbonate, leading to ongoing acid-base disorder.
Because chloride goes up as bicarbonate drops, the measured chloride may appear unexpectedly elevated. That pattern helps distinguish this disorder from a high-gap process. Still, mixed disorders can occur, so the calculator should be viewed as an element of a broader diagnostic algorithm.
In practice, recognizing hyperchloremia alongside low bicarbonate can help pinpoint the cause of metabolic acidosis and prevent overlooking a normal-gap pattern that calls for a different workup than lactic acidosis or ketoacidosis.
How Albumin Affects the Anion Gap
Serum albumin is a major factor to the body’s nonmeasured negative electrical charge. As a result, hypoalbuminemia can reduce the measured anion gap even when acid accumulation is present. This is why albumin-corrected anion gap values are so helpful in clinical interpretation.
The association is rooted in protein charge: albumin carries negative charge at physiologic pH, so when albumin falls, the measured gap may also fall. In patients with critical illness, low albumin is frequent, which makes uncorrected results less dependable.
Albumin correction assists clinicians avoid a false sense of confidence. A patient with sepsis, shock, or organ failure may have a “normal” raw value but still carry a clinically significant high anion gap metabolic acidosis once the correction is applied.
For this reason, many clinicians choose using a calculator that includes plasma albumin or serum albumin as an input. That approach strengthens the usefulness of the anion gap calculation as a day-to-day screening tool and aids better detection of unmeasured acid burden.
Clinical Mistakes and Typical Computation Errors
Various issues can make an otherwise useful result inaccurate. One common issue is laboratory error, including sample contamination, delayed processing, or an analyzer problem. If the result does not fit the Visit this website patient’s condition, rechecking is important.
One other mistake is failing to recognize mixed acid-base disorders. A patient may have both an elevated gap and a concurrent metabolic process that hides the expected bicarbonate change. This is especially relevant in complex hospitalized patients.
Potassium omission is another cause of confusion. If a calculator includes potassium and the clinician expects a sodium-only formula, the numbers will not match. Always know which anion gap formula is being used.
Unit mismatch can also distort the calculation. Input values must be in the correct units, and the calculator should not be fed values from different reporting systems without confirmation. Even small entry errors can create an incorrect impression of a major electrolyte disturbance.
Best clinical practice is to treat the calculator as one part of an acid-base analysis, not the final answer. If the result is unexpected, recheck the raw electrolytes, review the chart, and compare the trend with prior laboratory values.
When to Recheck Labs or Order Additional Testing
Additional testing is appropriate when the anion gap does not match the clinical picture, when the patient appears unstable, or when the result suggests a serious metabolic derangement. A repeat panel can help confirm whether the abnormality is persistent or due to transient variation.
An arterial blood gas is useful when you need a broader assessment of acid-base status, including pH and respiratory compensation. This is especially helpful if the bicarbonate value and clinical findings do not align.
Other targeted studies may include serum lactate when lactic acidosis is considered, or ketones when ketoacidosis is possible. If the history suggests exposure of a harmful substance or an abnormal osmotically active compound, an osmolar gap may provide additional clues.
Repeating the test is also warranted if there is concern about laboratory error, sample handling issues, or a changing clinical condition such as evolving renal failure. The goal is to use the calculator as a prompt for focused workup, not as an endpoint.
When interpreted correctly, the tool can support timely decisions, improve recognition of metabolic acidosis, and support a more structured response to acid-base abnormalities.
FAQ About the Anion Gap
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the difference between measured cations and anions on a serum chemistry panel. In practice, it helps assess acid-base balance, identify possible unmeasured anions, and support evaluation of metabolic acidosis. It is most helpful as a screening tool and part of broader clinical interpretation.
What is a normal anion gap range?
The normal range depends on the laboratory method and whether the calculation includes potassium. Because of lab variation, the best comparison is the laboratory-specific reference range that accompanies the patient’s results. A normal number does not exclude all acid-base disorders, especially normal anion gap metabolic acidosis.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate. Some methods include potassium. The key is to use the same method as the calculator or laboratory report and check the units before interpreting the result.
Why should you correct the anion gap for albumin?
You account for to account for albumin because serum albumin is a key unmeasured anion. With hypoalbuminemia, the raw gap may appear falsely normal. An albumin-corrected anion gap helps reveal hidden acid build-up and strengthens the detection of high anion gap metabolic acidosis, especially in critical illness.
What situations cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and renal failure. Other causes exist, but these are among the most common and clinically important. When the gap is high, clinicians should search for the underlying source of acid production or impaired acid clearance and consider additional testing if needed.