What the Anion Gap Measures
The anion gap serves as a practical approach to approximate unmeasured ions in the blood and to support acid-base balance during a clinical workup. It’s usually derived from serum electrolytes, particularly serum sodium, serum chloride, and serum bicarbonate. As these values shift in predictable ways, the anion gap can reveal a hidden metabolic disturbance that would otherwise be missed on a basic chemistry panel.
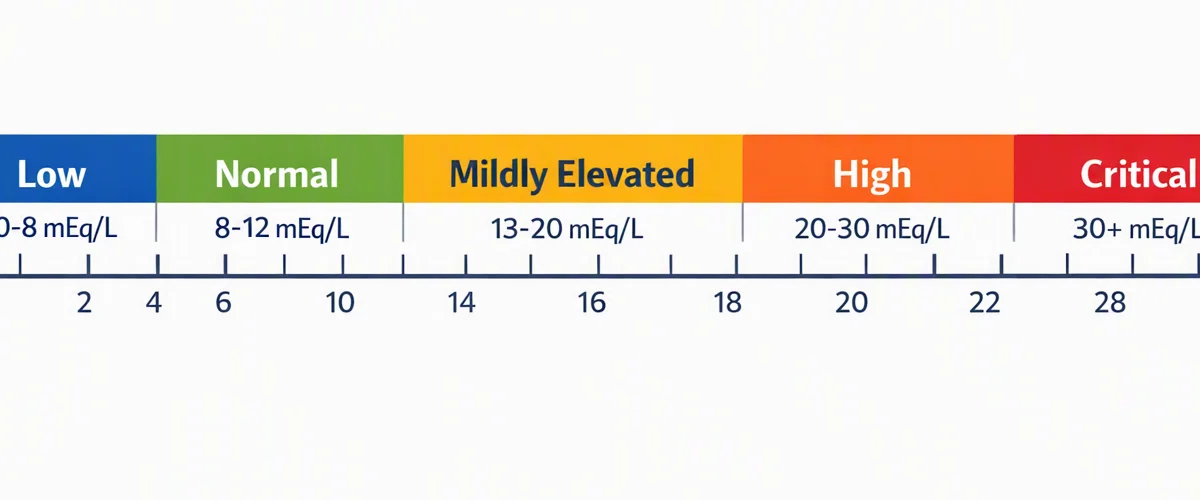
In everyday practice, clinicians use the anion gap as a diagnostic marker for acid accumulation. A above-normal value suggests that unmeasured acids are present in excess, often pointing toward metabolic acidosis. This makes the calculation very useful as an interpretation guide when evaluating an ill patient, a lab screening result, or a suspected electrolyte imbalance.
The basic anion gap formula typically removes chloride and bicarbonate from sodium. Some versions also include potassium, but the most commonly used approach excludes it for simplicity and consistency. An anion gap calculator automates this step, helping clinicians quickly calculate anion gap values and consider the bigger question: what process is driving the abnormality?
Because the calculation is based on measured ions, it is not a complete picture of physiology. Instead, it is a quick and useful approximation that supports laboratory assessment and more detailed acid-base interpretation. When the result is elevated, it often signals an elevated anion gap state that requires a closer look at renal function, perfusion, toxin exposure, and inherited metabolic disease.
Why Methylmalonic Acidemia Raises the Anion Gap
Methylmalonic acidemia is an organic-acid disorder and an hereditary metabolic disorder in which the body cannot properly break down certain metabolites, leading to the buildup of acids. That buildup causes metabolic acidosis and commonly results in a increased anion gap metabolic acidosis. In this setting, the anion gap becomes a indicator to the underlying biochemical problem rather than just a number on a report.
The core issue is that methylmalonic acid along with related compounds build up in the bloodstream. These acids consume buffering capacity, lower bicarbonate, and contribute to an excess of unmeasured anions. Therefore, the anion gap often increases alongside the severity of the acid-base disorder. This is why a calculator can be useful in identifying the pattern early, especially when the patient is critically ill and the presentation is not specific.
In methylmalonic acidemia, the overall picture Browse this site may suggest a metabolic emergency. Individuals can show vomiting, poor feeding, lethargy, dehydration, or encephalopathy, and the lab profile may show an elevated anion gap long before the full diagnosis is confirmed. The biochemical pattern usually shows accumulation of toxic metabolites, decreased energy metabolism, and secondary systemic stress. That is why an anion gap calculator can be a valuable first step in interpretation, but not the definitive step in diagnosis.
The connection between the derived gap and the disease process is greatest when the presentation includes acidosis along with other supportive signs. However, the anion gap alone does not establish methylmalonic acidemia. It functions as a clinical correlation resource that helps clinicians identify a profile consistent with an organic acid accumulation and proceed to targeted workup.
How to Use an Anion Gap Calculator
When using an anion gap calculator, provide the essential serum electrolytes: serum sodium, serum chloride, and serum bicarbonate. Many tools also support entry of potassium and albumin. The calculator runs the selected formula and produces the observed gap, which can then be compared with the expected range for the lab.
When potassium is included, the formula may produce a slightly higher value. In many clinical settings, however, potassium is omitted because it contributes less to everyday decision-making and can vary between institutions. The more important step is to recognize whether the result suggests an elevated anion gap and whether that elevation matches the rest of the patient’s picture.
Albumin matters because it is a major unmeasured anion. Low albumin can make the anion gap appear falsely normal or only mildly elevated. That is why many clinicians apply albumin correction to estimate a corrected anion gap. This is especially important in patients with malnutrition, inflammation, liver disease, or prolonged illness, where hypoalbuminemia can mask the degree of acidosis.
A simple ordered approach looks like this:
- Add the available serum electrolytes into the calculator. Assess whether the result indicates a high or normal gap. Check albumin and apply albumin correction if needed. Compare the result with the clinical setting and other labs. Use the number as part of broader acid-base interpretation, not as a standalone answer.
Used properly, the calculator helps guide the workup and supports a more accurate assessment of acid-base balance. It is most useful when paired with symptoms, kidney function, ketones, lactate, and a blood gas.
Explaining Elevated Anion Gap Values
A elevated anion gap metabolic acidosis shows that undetected acids are piling up. In the evaluation, the most common categories include lactic acidosis, ketoacidosis, and toxin exposure. These conditions can interact with methylmalonic acidemia or mask it, so interpretation should always be clinical rather than formulaic.
Lactic acidosis may occur with poor perfusion, circulatory collapse, hypoxemia, seizures, or severe illness. It produces excess lactate, which widens the gap. Ketoacidosis occurs in diabetes, prolonged fasting, or starvation states, and the ketone bodies drive the elevated gap. Both can coexist with other metabolic abnormalities, making the final pattern less straightforward than a single diagnosis.
Toxin exposure should also be kept in mind when the gap is high. Salicylates, toxic alcohols, and other poisons may generate a substantial acid burden. In suspected ingestion, the anion gap is a useful clue but not the endpoint. Osmolal gap testing, toxicology studies, and serial blood gas data may be needed for a full picture.
For methylmalonic acidemia, the key point is that a high anion gap can be a sign of organic acid buildup, but not every elevated gap is caused by an organic acidemia. A structured assessment helps separate the biochemical pattern from the underlying cause. The calculator can identify the abnormality, but interpretation requires the full context of illness severity, nutrition status, renal function, and timing of collection.
Correction of the Anion Gap & Clinical Setting
Raw anion gap results can be deceptive unless the larger acid-base disorder is taken into account. Here is where correction for albumin becomes important. As albumin is negatively ionized, low levels reduce the baseline gap. A patient with marked acidosis and hypoalbuminemia may therefore show a apparently normal result unless the value is corrected.
Correcting for albumin increases the utility of the anion gap calculator and makes the number more reflective of true acid burden. This matters especially in critically ill patients, where low albumin is common and physiologic compensation may partially offset pH changes. A normal pH does not rule out acidosis if compensation is present.
This is why blood gas analysis is such an important companion test. A blood gas can establish pH, bicarbonate status, and compensatory respiratory changes. Combined with the corrected gap, it helps define whether the patient has primary metabolic acidosis, a superimposed respiratory process, or a combined acid-base disorder.
Practically speaking, clinicians should avoid interpreting the anion gap in isolation. The most accurate approach integrates albumin, serum chemistry, blood gas analysis, symptoms, and time course. That complete review can separate an acute metabolic emergency from a chronic compensated state and can prevent under-recognition of severe disease.
Lab Findings in Methylmalonic Acidemia
Multiple test results point to the diagnosis of methylmalonic acidemia. The clearest is elevated methylmalonic acid, which reflects the underlying enzymatic block and supports the presence of excess abnormal metabolites. This finding often is associated with a high anion gap state, but the magnitude of the gap can fluctuate depending on hydration, nutrition, and concurrent illness.
Cobalamin deficiency is a key related consideration because vitamin B12 metabolism is tightly linked to methylmalonic acid handling. In some patients, low B12 or impaired cobalamin processing adds to the biochemical picture. This is why methylmalonic acidemia and cobalamin-related disorders are often assessed together during a laboratory assessment.
Ammonia may also be elevated, especially during decompensation. Hyperammonemia can aggravate neurologic symptoms and heighten the concern for a metabolic crisis. Likewise, ketones may be present as the body shifts toward alternative fuels during stress or inadequate intake. These findings reinforce the suspicion of a serious inherited metabolic disorder.
When all these results are viewed together, the pattern stands out more clearly: elevated methylmalonic acid, possible cobalamin involvement, increased ammonia, and ketosis can accompany a high anion gap. The result is a biochemical pattern that clearly supports further metabolic testing and urgent clinical correlation.
Common Differential Diagnoses
A number of conditions can resemble methylmalonic acidemia on early assessment. Propionic acidemia is one of the most important because it is another organic acidemia with similar features, including acidosis, ketosis, and an high gap. Telling apart these conditions usually requires targeted biochemical and genetic evaluation rather than a single electrolyte panel.
Renal failure is another common cause of high anion gap acidosis. When kidney function declines, acids accumulate and unmeasured anions rise. In this setting, the anion gap may be elevated for reasons unrelated to an inborn error of metabolism, so renal markers and the overall clinical context are important.
Sepsis can also cause a high-gap picture through lactic acidosis, anion gap clinical significance poor perfusion, and multiorgan stress. Because sepsis can present with nonspecific symptoms and rapid decompensation, it can overlap clinically with metabolic disease. A clinician evaluating a patient with suspected methylmalonic acidemia should always consider infection as a trigger or an alternate explanation.
More broadly, the category of inborn errors of metabolism includes many conditions that present with acidosis, hyperammonemia, and neurologic changes. Anion Gap Calculator is useful for assessing the acid-base pattern, but the differential diagnosis must remain wide until confirmatory studies narrow it down.
When the Anion Gap May Be Deceptive
Even though the anion gap is useful, it is not infallible. A patient with significant disease may still show a normal anion gap if the issue is masked by low albumin, early sampling, or concurrent alkalinizing processes. In methylmalonic acidemia, this can happen if the patient has had fluid therapy, is partially treated, or is in a milder phase of illness.
Mixed acid-base disorders are among the most critical pitfalls. For example, a patient may have metabolic acidosis from organic acid accumulation and a concurrent respiratory alkalosis from hyperventilation. The pH can look near normal even though the underlying disturbance is substantial. Blood gas interpretation is therefore essential.
Hypoalbuminemia can lower the apparent gap to the point to hide the severity of the disorder. This is why albumin correction is so important. If albumin is low and the corrected result becomes obviously abnormal, the concern for an organic acid process rises significantly.
Laboratory variation can also affect the result. Small differences in analyzer method, specimen handling, or repeat sampling can change the number slightly. For that reason, a single borderline value should not be read too much into. Trend data, the clinical picture, and repeat testing are often more useful than one isolated result.
In short, the anion gap is a helpful indicator, not a diagnosis. The best interpretation comes from integrating the calculator output with blood gas analysis, albumin status, symptoms, and the broader biochemical pattern.
Frequently Asked Questions
How does an anion gap calculator help in methylmalonic acidemia?
An anion gap calculator helps by quickly identifying whether the patient has an elevated gap consistent with metabolic acidosis. In methylmalonic acidemia, this supports recognition of organic acid buildup and helps guide further testing. It is a valuable screening tool, but it does not replace clinical evaluation or confirm the diagnosis on its own.
Which anion gap formula is best used for serum electrolytes?
The standard anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Some formulas include potassium, but many clinical calculators omit it. The preferred choice is the one that matches the laboratory and the clinician’s assessment method for serum electrolytes.
Does methylmalonic acidemia cause a normal anion gap?
Indeed. Methylmalonic acidemia can at times occur with a normal anion gap, especially if there is hypoalbuminemia, early disease, treatment effects, or a mixed acid-base disorder. That is why the calculator should be paired with albumin correction and blood gas analysis.
For what reason is albumin correction important when interpreting the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap look falsely normal. Albumin correction helps estimate the true corrected anion gap and improves acid-base interpretation. This is especially important in illness, where hypoalbuminemia can mask a significant high anion gap metabolic acidosis.
What additional conditions can look like methylmalonic acidemia on an anion gap test?
Common mimics include propionic acidemia, renal failure, sepsis, lactic acidosis, ketosis, and other inborn errors of metabolism. Toxin exposure can also produce a similar pattern. The anion gap is helpful for spotting the biochemical pattern, but the final diagnosis depends on the whole laboratory and clinical picture.