An Anion Gap Calculator can turn a routine set of blood test results into a valuable clue about acid-base balance. In blood chemistry evaluation, the anion gap helps clinicians determine whether a patient may have a metabolic derangement, especially one related to metabolic acidosis. It is not a diagnosis by itself, but it is a reliable screening tool that can indicate unmeasured anions, aid differential diagnosis, and help interpret results alongside other lab values.
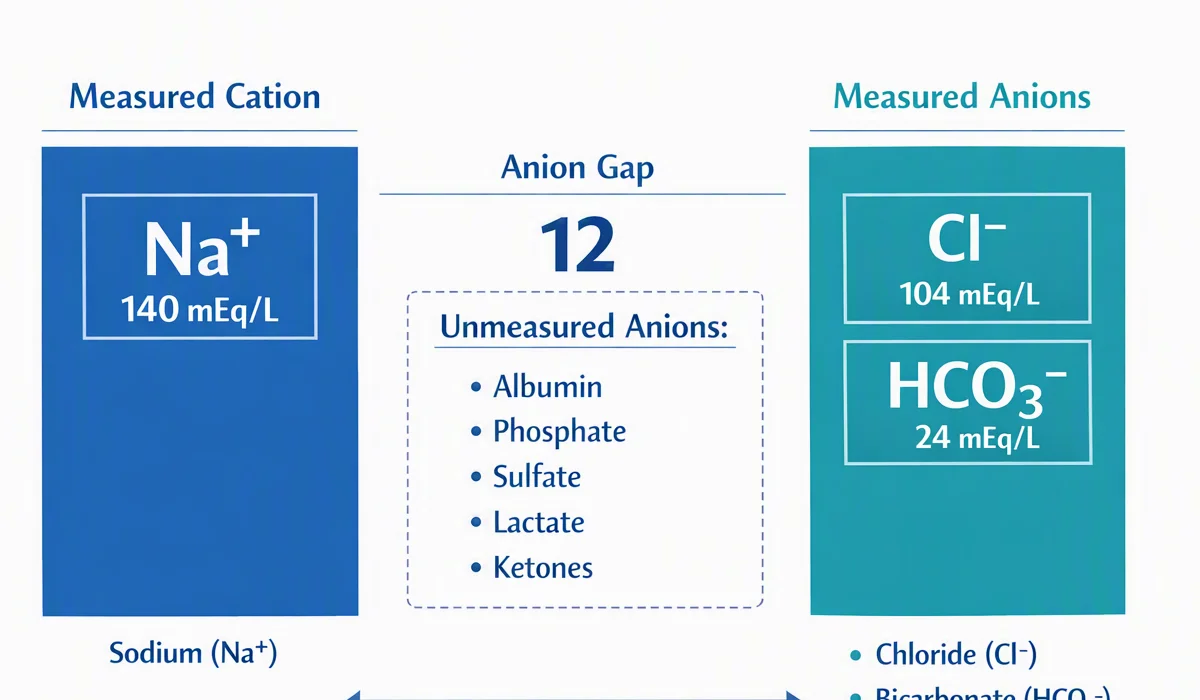
The anion gap is calculated from common electrolytes on a serum chemistry panel. Because it uses serum sodium, serum chloride, and serum bicarbonate, it is straightforward to estimate from a standard blood chemistry panel. In the right clinical setting, the anion gap value can help distinguish high anion gap metabolic acidosis from normal anion gap metabolic acidosis and reveal when albumin adjustment is needed.
What the Anion Gap Measures
The gap calculation indicates the balance between cations that are measured and anions that are measured in the blood. It is based on the idea that the body’s electrolytes must remain electrically neutral. As not all ions are directly measured on a routine electrolyte panel, the calculation calculates the gap between what is measured and what is not.
The primary elements are serum sodium, serum chloride, and serum bicarbonate. Sodium is the principal measured cation included in the formula, while chloride and bicarbonate are the main measured anions. Potassium is at times included, but many clinicians use a basic version that excludes it because potassium contributes very little to the final number.
In clinical interpretation, the anion gap is most valuable as a diagnostic marker for acid-base disorder. A changed anion gap may suggest the presence of unmeasured anions such as lactate, ketones, or toxins. That makes it highly useful in blood chemistry analysis when evaluating unclear metabolic acidosis or electrolyte imbalance.
In simple terms, the test helps answer this question: does the blood chemistry pattern indicate extra acids are present, or is the problem due to bicarbonate loss with a normal gap? That distinction matters because high anion gap metabolic acidosis and normal anion gap metabolic acidosis usually lead clinicians down distinct diagnostic pathways.
How to Use an Anion Gap Calculator
An Anion Gap Calculator is designed to make the calculation formula fast and reliable. The calculator typically asks for three core calculator inputs: serum sodium, serum chloride, and serum bicarbonate. Some versions also include an option to account for potassium or to correct for albumin.
Using the calculator is straightforward. Enter the blood chemistry results from the electrolyte panel, and the tool returns the anion gap value. This can then be checked against the expected normal range or reference interval used by the laboratory. Because reference ranges fluctuate slightly by method and lab values, it is important to interpret the result in context rather than relying on a single universal cutoff.
A calculator is useful because it minimizes arithmetic mistakes and supports more consistent clinical interpretation. It can also help clinicians and patients quickly review results from a blood chemistry panel without needing to manually apply the calculation formula every time.
Typical steps include:
- Review the blood chemistry panel for serum sodium, serum chloride, and serum bicarbonate. Submit the calculator inputs exactly as reported by the laboratory. Check whether potassium should be included based on the calculator design or local practice. Match the result to the reference interval used by that laboratory. Review albumin adjustment if serum albumin is low or if the clinical picture suggests hypoalbuminemia.
The best use of the calculator is not just to arrive at a number, but to interpret that number with the rest of the serum chemistry and the patient’s clinical presentation.
Anion Gap Formula and Step-by-Step Calculation
The standard anion gap formula typically used is:
Anion gap = Na+ - (Cl- + HCO3-)
Here, Na+ stands for serum sodium, Cl- indicates serum chloride, and HCO3- stands for serum bicarbonate. This formula is the basis for most Anion Gap Calculator tools. In some settings, potassium is added:
Anion gap = (Na+ + K+) - (Cl- + HCO3-)
Including potassium somewhat increases the reported value, but many clinical references prefer the version without potassium because it is easier to use and is still clinically helpful.
Step by step, the process is simple:
- Take the serum sodium value from the blood chemistry analysis. Add serum chloride and serum bicarbonate together. Deduct that sum from sodium. If using potassium, add potassium to sodium before subtracting the other electrolytes.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap equals 140 - (102 + 24) = 14. If potassium is included, the calculation becomes 140 + 4 - (102 + 24) = 18. The result depends on the formula used, which is why the method should always be matched to the calculator or lab reference interval.
Understanding the calculation formula also helps clinicians detect unexpected lab values. If the anion gap seems inconsistent with the rest of the electrolyte panel, that may point toward a measurement issue, albumin effect, or another acid-base disorder.
Standard Anion Gap Range and What Counts as High or Low
The reference range for anion gap is based on the reference interval used by the laboratory. Different methods, analyzers, and whether potassium is included can all affect the reported normal range. That is why clinicians should interpret results using local lab values, not a single universal threshold.
In general, a result above the expected range is classified a high anion gap, while a result below the normal range is considered a reduced anion gap. However, lab variation is important. Slight differences in measurement process, sample processing, or analyzer calibration can alter the range slightly.

A elevated anion gap is clinically significant because it can signal build-up of unmeasured anions associated with metabolic acidosis. A low anion gap is uncommon, but it can indicate hypoalbuminemia, paraproteins such as the ones seen in multiple myeloma, lithium toxicity, or laboratory error.
Key points to note:
- Reference range: Always use the lab’s own interval when possible. High anion gap: Often suggests increased acid load or undetected anions. Low anion gap: May be caused by low albumin or other uncommon causes. Laboratory variation: Different analyzers can report somewhat different results.
In practical clinical interpretation, the anion gap is most valuable when followed over time or when paired with related blood test results. One isolated number should rarely be interpreted by itself.
Albumin Correction and Why It Is Important
Serum albumin has a major effect on the anion gap because it is a negative protein in the blood. When serum albumin is low, the measured anion gap may appear incorrectly normal or even low. That is why albumin correction is so important in blood chemistry analysis.
Hypoalbuminemia lowers the number of unmeasured anions in the blood, which lowers the apparent anion gap. As a result, a patient may actually have a important acid-base problem that is hidden unless the corrected anion gap is calculated. The corrected anion gap adjusts for this using an albumin adjustment or correction formula.
The corrected anion gap is particularly important when evaluating metabolic acidosis in patients with low serum albumin, chronic illness, inflammation, or poor nutrition. In these cases, the uncorrected value may miss the severity of the disorder.
Protein binding also matters because albumin is part of the body’s overall electrical balance. When protein binding changes, the apparent distribution of ions can vary, affecting the clinical interpretation of lab values. That is why clinicians often review serum albumin before making strong conclusions from an anion gap value.
In practice, albumin correction improves the usefulness of the Anion Gap Calculator by making the result more precise. It can reveal hidden high anion gap metabolic acidosis that would otherwise be missed and can also reduce confusion when a low or borderline result appears discordant with the rest of the serum chemistry.
Reasons for a High Anion Gap
A increased anion gap often suggests an acid buildup caused by increase of unmeasured anions. This is the classic setting where the anion gap is most helpful as a clinical marker. Clinicians often use it to refine the differential diagnosis when blood chemistry results show a reduced bicarbonate level and an increased gap.
Common causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactate accumulates when tissues are poorly perfused or not using oxygen effectively. Ketoacidosis occurs when ketones build up, often in diabetes, starvation, or heavy alcohol use. Renal failure can reduce the body’s ability to clear acids, allowing unmeasured anions to rise.
High anion gap metabolic acidosis is typically identified when the bicarbonate level falls and the gap rises over the reference interval. In this situation, the blood chemistry pattern points toward an acid-base disorder that needs further investigation rather than a simple electrolyte imbalance.
Frequent high-gap patterns include:
- Lactic acidosis: Often associated with shock, hypoperfusion, or severe illness. Ketoacidosis: Might occur in diabetes, fasting, or alcohol-related states. Renal failure: Reduced acid clearance can increase the anion gap.
Although the Anion Gap Calculator can show the pattern, it does not identify the exact cause. Clinical context, symptoms, medication history, and other lab values are needed to determine the underlying diagnosis.
Causes of a Low Anion Gap
A reduced anion gap is less common than a increased one, but it can still be clinically meaningful. A key cause to consider is hypoalbuminemia, because low serum albumin is the most common reason for a reduced calculated value. When albumin is decreased, the anion gap can drop even when the underlying acid-base status is not truly normal.
Additional causes include multiple myeloma, lithium toxicity, and laboratory error. In multiple myeloma, unusual positively charged proteins can alter the balance of measured ions. Lithium toxicity can introduce excess unmeasured cations, lowering the gap. Laboratory error is always a possibility and should be considered whenever the result does not match the clinical picture.
A low anion gap result should prompt a careful review of the electrolyte panel, serum albumin, and the overall serum chemistry. If the result is unexpected, clinicians may compare it with prior blood test results or repeat the test to confirm whether the finding is real.
Typical causes of a low gap include:
- Hypoalbuminemia: The leading explanation. Multiple myeloma: May lead to abnormal proteins that affect interpretation. Lithium toxicity: Can lower the anion gap through excess cations. Laboratory error: Should always be excluded if the number is surprising.
A low value is not always benign, and its interpretation depends on the full clinical interpretation of the patient’s lab values and symptoms.
How Clinicians Interpret the Result in Context
Clinicians rarely interpret the anion gap by itself. Instead, they connect it to the arterial blood gas, the osmolar gap, and the broader pattern of acid-base disorders. This approach improves diagnostic accuracy and helps distinguish among overlapping conditions.
An arterial blood gas can confirm whether there is acidemia or alkalemia and whether the primary issue is metabolic or respiratory. The osmolar gap may help identify toxic alcohol exposure or other causes of unexplained metabolic acidosis. The delta gap can reveal mixed acid-base disorders by comparing the change in anion gap to the change in bicarbonate.
This systematic approach is particularly helpful when the chemistry panel indicates high anion gap metabolic acidosis. For instance, a high gap with low bicarbonate and an abnormal arterial blood gas may strongly support a serious acid-base disorder. If the delta gap suggests a mismatch, there may be more than one mechanism happening simultaneously.
Clinicians rely on the anion gap as part of a broader clinical assessment, not as a stand-alone answer. For that reason a calculator should be treated as a preliminary tool that supports clinical interpretation rather than taking the place of judgment.
In many cases, the trend is more important than the exact number. A slight change may matter if it is new, while a higher value may be less alarming if it is long-standing and explained by known hypoalbuminemia or another stable condition.
Drawbacks, Cautions, and When to Recheck Labs
Even a well-designed Anion Gap Calculator has drawbacks. The result depends on precise lab values, and issues can arise from preanalytical error, assay artifact, or specimen handling problems. As a result, unusual https://anion-gap-calculation.com/calculators/corrected-anion-gap.html results should be interpreted cautiously.
Pre-analytical error can arise before the sample even gets to the analyzer. Delays, sample contamination, poor collection, or handling issues may alter the electrolyte panel. Measurement artifact may come from analyzer-specific differences or confounding effects from unusual substances in the sample.
Repeat testing is often appropriate when the anion gap is unexpectedly high or low, especially if the patient has no symptoms that match the result. Rechecking labs can help confirm whether the electrolyte imbalance is real or whether the number was affected by a transient issue.
Situations that justify a repeat test include:
- The result is inconsistent with the clinical picture. There is concern for laboratory error or measurement artifact. The patient has a sudden change in status or an unexplained metabolic derangement. Prior blood test results were normal and the new value is surprising.
It is important to keep in mind that the anion gap is affected by albumin, assay-specific reference interval differences, and the way the calculator sets out the formula. Minor variations can change interpretation, especially near the cutoff range. Careful review of lab values, albumin, and the patient’s overall condition is the safest way to avoid misreading.
FAQ About the Anion Gap Calculator
What does an anion gap calculator used for
An Anion Gap Calculator is used to interpret blood chemistry analysis by determining the anion gap from electrolyte values. It is frequently used to check metabolic acidosis, identify high anion gap metabolic acidosis, and support clinical interpretation of acid-base disorders. It also helps doctors decide when albumin correction may be needed.
How can you calculate the anion gap from blood chemistry results?
The standard formula used for calculation is anion gap = Na+ - (Cl- + HCO3-). Some approaches add potassium, with anion gap = (Na+ + K+) - (Cl- + HCO3-). The calculator inputs are usually serum sodium, serum chloride, and serum bicarbonate from the blood chemistry panel. Potassium may or may not be included depending on the method being used.
How much is a typical anion gap value?
A normal anion gap value depends on the laboratory reference range and the equation used. Since laboratory variation exists, the most accurate approach is to evaluate the result with the reference interval provided by the lab. A value higher than that range is considered increased, and a value less than it is considered reduced.
Why is albumin correction important for the anion gap?
Correcting albumin is important because reduced serum albumin can depress the measured anion gap and hide clinically important metabolic acidosis. A corrected anion gap uses an albumin compensation formula to more precisely show unmeasured anions. This makes interpretation easier when hypoalbuminemia is present.
What causes a high or low anion gap?
A elevated anion gap is often due to lactic acid buildup, ketosis-related acidosis, or kidney failure and usually suggests metabolic acidosis with unmeasured anions. A reduced anion gap is frequently due to low albumin, but it can also occur with multiple myeloma, lithium overdose, or testing error. The result should always read in the context of clinical findings and the rest of the chemistry panel.