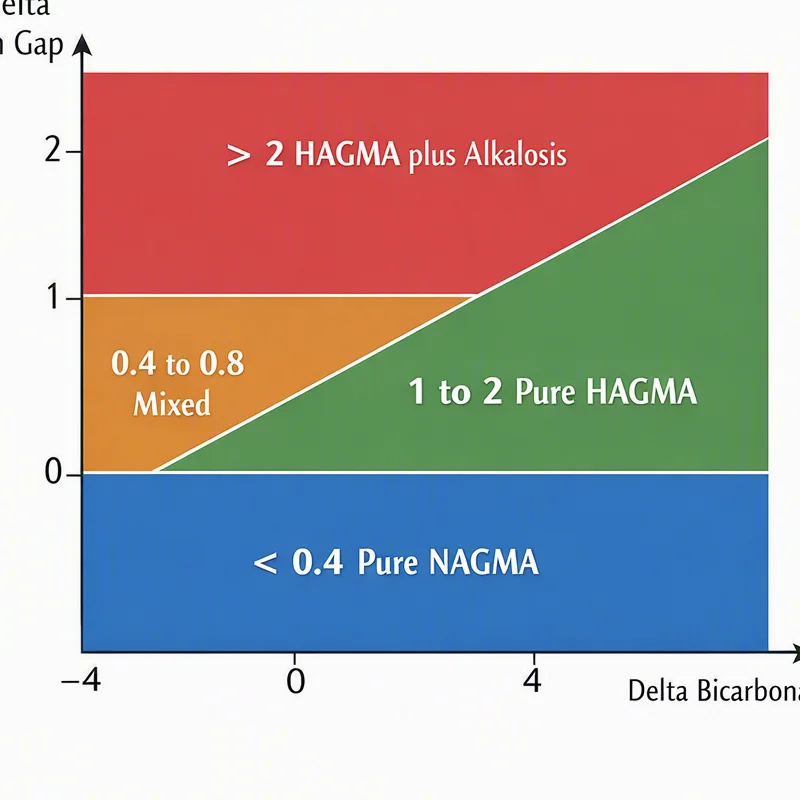
How this Anion Gap Evaluates
The anion gap is a straightforward way to estimate the difference between measured positive and negatively charged particles in the blood. It is most often used as a diagnostic tool for identifying an electrolyte imbalance and helping evaluate metabolic acidosis. By examining common electrolytes such as sodium, chloride, and bicarbonate, clinicians can infer whether there are extra unmeasured anions present in the bloodstream.
This matters because the body depends on tight acid-base balance to keep cells functioning normally. When that balance shifts, the change may indicate an underlying acid-base disorder, a metabolic disturbance, or a problem with kidney function. An anion gap result does not identify a condition by itself, but it can guide the next step in evaluation.
The anion gap is determined from serum electrolytes and other values reported on a blood chemistry or electrolyte panel. Because it is based on routine blood tests, it is widely used in routine follow-up. In practice, the number helps identify whether the blood contains excess acids, such as organic acids, or whether a low result is due to missing proteins like albumin.
How to Operate an Anion Gap Calculator
An anion gap calculator is a quick calculation aid that relies on values from a standard chemistry panel. The usual inputs are sodium, chloride, and bicarbonate, and some versions also include potassium. The calculator then applies a formula to estimate the gap and compare it with a normal reference range.
To use the calculator correctly, type in the measured lab values exactly as reported. Small changes in one input can shift the result, especially when the overall anion concentration is close to the normal range. Since the output is only as accurate as the data entered, it is crucial to confirm the numbers from the serum chemistry report and not from memory.
A practical workflow is:
- Obtain the values from the electrolyte panel. Determine whether the calculator uses the standard or potassium-included method. Input sodium, chloride, bicarbonate, and potassium if needed. Interpret the result in the context of the patient’s symptoms and other blood tests.
The calculator is a preliminary and analysis aid, not a replacement for clinical interpretation. A single number should always be reviewed alongside the full clinical picture, including medications, hydration status, and signs of acid-base disorders.
When Potassium Is Counted in the Calculation
Potassium is at times brought in because it is also a cation in the blood and can be factored in in the relationship between measured ions. The classic or traditional anion gap calculation usually excludes potassium because its concentration is relatively small compared with sodium. However, a modified anion gap accounts for potassium and can produce a slightly higher result.
The difference is notable when comparing calculators or reading older literature. If potassium is included, the calculated gap will anion gap clinical significance usually rise by a few units, but the clinical meaning may still be similar. That is why a result must always be interpreted based on which formula was used.
There are circumstances where the potassium-included method may be preferred, especially in analytical discussions of acid-base balance or when a system is designed to account for all major measured cations. Even then, most bedside and routine references still rely on the traditional anion gap, so uniformity matters more than the specific method itself.
In simple terms, the potassium-included version is a modified anion gap approach that adds one more measured electrolyte to the calculation. The result can be informative, but it should not be mixed with standard reference values from a calculator that excludes potassium.
Formula for Anion Gap and Step-by-Step Calculation
The computational formula is determined by whether potassium is included. The usual traditional form is:
Anion gap = sodium - (chloride + bicarbonate)
With potassium included, the formula changes to:
Modified anion gap = sodium + potassium - (chloride + bicarbonate)
These equations use serum electrolytes from a routine blood chemistry panel. For a full interpretation, it can also be useful to review albumin, since albumin is a major unmeasured anion and a low level can reduce the apparent gap.
Here is a step-by-step example using the potassium-included method:
- Start with the measured sodium. Include potassium if the calculator uses the modified method. Add together chloride and bicarbonate. Subtract the chloride-bicarbonate total from the sodium-plus-potassium total.
For example: if sodium is 140, potassium is 4, chloride is 102, and bicarbonate is 24, then the modified anion gap is 140 + 4 - (102 + 24) = 18.
The calculated value should then be checked against the correct baseline value for the specific formula used. If albumin is low, a correction may be needed because the raw number can underestimate the severity of a metabolic problem. For that reason the calculator is only the starting point, not the final answer.
Standard Range and The Meaning of High or Low Values
The normal range depends on the laboratory method and on whether potassium is included. For the standard anion gap, many expected values sit in a small interval, while the potassium-adjusted version is typically a few units higher. A calculator should display the method clearly so the result is read against the correct normal range.
A high anion gap often points to extra acids or unmeasured anions in the blood. This can happen in a number of serious conditions and often points toward a metabolic acidosis. A low anion gap is less common, but when present it can suggest low albumin, analytical issues, or other unusual protein changes.
Determining whether the value is slightly abnormal or clearly outside the expected range is part of good clinical interpretation. A small shift may suggest minor variation in blood test results, while a more pronounced abnormality can signal a true acid-base disorder.
The most useful approach is to compare the number with the patient’s overall condition, the rest of the electrolyte results, and related findings such as kidney markers and acid levels. In other words, the calculator returns a number, but the clinician gives meaning to that number.
Common Reasons of an Elevated Anion Gap
A elevated anion gap usually indicates there are more not measured anions in the blood. Among the most frequent causes is lactic acidosis, which develops when the body generates or eliminates lactate badly. This usually points to tissue hypoxia, severe illness, or an additional process that adds to acid load.
Ketoacidosis is another important cause. In this situation, ketone bodies collect and elevate the gap. It may occur with diabetes, starvation, or prolonged alcohol use. Because ketones are organic acids, the anion gap can increase as bicarbonate is consumed during buffering.
Renal failure can also cause the gap to rise because the kidneys are not as able to excrete acids. Reduced kidney performance leads to retention of acid and other metabolic byproducts, which can contribute to acidosis. This makes the anion gap a valuable clue in evaluating kidney-related metabolic disturbance.
Additional important causes include toxic alcohols, which are classic considerations in a serious unexplained acidosis. These substances may generate metabolites that increase the gap and can require urgent attention. A high result should therefore prompt a careful review of history, medication exposure, symptoms, and other blood tests.
Common Causes of a reduced anion gap
A low anion gap is uncommon and often deserves a careful review rather than quickly brushing it aside. The most frequent reason is hypoalbuminemia. Since albumin plays a major role to the unmeasured anion pool, a decreased albumin level can lower the gap even when other chemistry values seem ordinary.
Laboratory error is another major possibility. Because the anion gap is calculated from other values, any mistake in sodium, chloride, or bicarbonate can distort the final answer. Repeating the blood test may be reasonable when the result does not align with the clinical picture.
Paraproteinemia, such as in certain plasma cell disorders, can also decrease the gap. In these conditions, abnormal proteins may act differently than expected and shift the balance of measured and unmeasured ions. This is one reason the anion gap is valuable as a screening clue rather than a single diagnosis.
In some cases, a low gap reflects a blend of factors, including low albumin, changes in serum electrolytes, or atypical blood chemistry patterns. The key is to evaluate the result in the broader context of the patient’s symptoms and full clinical interpretation.
Drawbacks of the Calculator and Clinical Context
An anion gap calculator is helpful, but it has drawbacks. It relies on measured values from blood tests and cannot account for each source of acid-base change. A normal result does not exclude all acid-base disorders, and an abnormal result does not determine the exact cause on its own.
Another limitation is that different laboratories may use different analytic methods, which can change the reference range. That means the same patient may show a slightly different result depending on the instrument, reporting style, or whether the formula includes potassium. The calculator should therefore be used as a screening and interpretation aid, not as a final diagnostic endpoint.
Clinical context counts just as much as the number itself. Symptoms, physical exam findings, medication use, kidney function, and the rest of the electrolyte panel all affect interpretation. For ethylene glycol high AG example, a modestly elevated gap in a patient with suspected metabolic acidosis may be more meaningful than the same value in someone with no symptoms.
Good clinical interpretation also depends on whether the result is being compared with a baseline value. A change from the patient’s usual pattern may be significant even if the number still falls within a typical range. For this reason, the calculator is best viewed as one part of a broader diagnostic toolset.
FAQs About the Anion Gap Calculator
What is an anion gap calculator with potassium included?
An anion gap calculator with potassium included is a tool that estimates the gap using sodium, chloride, bicarbonate, and potassium. It uses a modified anion gap formula rather than the traditional one. This version can be beneficial when you want a more complete accounting of measured electrolytes.
Why would potassium be included in the anion gap formula?
Potassium may be factored in because it is a measured cation and plays a role in the overall ion balance. Factoring it in creates a modified anion gap that may be relevant in some clinical settings. However, most routine clinical references still use the traditional anion gap, so the formula must align with the reference range being used.
What would be the normal anion gap range when potassium is included?
The normal range is increased when potassium is included because the formula adds one more cation. The exact range depends on the laboratory and the calculator method. Always compare the result with the reference range provided for the specific formula, not with a standard range from a calculator that excludes potassium.
What may a high anion gap indicate?
A high anion gap often indicates additional acids in the blood, which can occur in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols. It usually points toward some form of metabolic acidosis. The exact cause depends on the rest of the labs and the overall clinical picture.
Can a normal anion gap still mean there is a medical problem?
Yes. A normal result does not exclude a medical issue, because not every acid-base disorder changes the gap. Some conditions cause a non-gap metabolic acidosis, while others may be present despite a normal calculation. The result should always be interpreted alongside symptoms, other blood chemistry values, and the full electrolyte panel.