What Is the Anion Gap?
The anion gap is a calculated measurement used to check electrolytes in the body and to support assessment of an acid-base disorder. It is not a directly recorded lab result. Instead, it is worked out from common blood chemistry results, usually including sodium, chloride, and bicarbonate. In some settings, potassium may also be added in the computation.
Clinicians employ the anion gap to look for a occult metabolic disturbance, especially when there is concern for metabolic acidosis. A elevated value can point to extra unmeasured acids in the blood, while a low value can suggest issues such as low serum albumin or laboratory differences. Because the calculation depends on routine serum electrolytes, it is often part of the broader medical assessment of a patient with abnormal blood chemistry.
In basic terms, the anion gap helps clinicians interpret how positively and negatively charged particles in the blood are offsetting each other. That balance is part of normal acid-base balance, and a change can be an valuable clue when reviewing laboratory results.
How an Anion Gap Calculator Operates
An Anion Gap Calculator is an instrument that relies on lab values from a chemistry panel to estimate the anion gap rapidly and reliably. The calculator generally takes the measured concentrations of sodium, chloride, and bicarbonate, and in some versions also includes potassium. It then follows the standard anion gap calculation formula to deliver a numerical result.
For example, a common formula is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula may be adjusted slightly. Because the calculation is based on lab values, the result reflects the quality of the sample and the accuracy of the testing method. That is why the calculator is best used as part of broader clinical interpretation, not as a stand-alone diagnosis.
An Anion Gap Calculator is especially useful when reviewing a possible electrolyte imbalance or acid-base disorder. It can help identify a high anion gap or low anion gap pattern that deserves closer attention. In pediatric care, the calculator should be paired with the child’s age, symptoms, and other blood chemistry findings to support a more accurate conclusion.
Do Children Have Different Anion Gap Intervals Than Adults?
Absolutely, young patients can show varying ranges for the anion gap versus adults. The concept of a normal range is not always the same across every age, because children are not simply smaller adults. Maturation, metabolism, and hydration status change over time, so the appropriate reference range may vary by age and by laboratory.
In practice, clinicians often consider age-based reference ranges or a children’s reference interval when reviewing results in children and adolescents. Some laboratories use a slightly different reference interval for younger patients, while others apply the same overall interval across age groups but advise caution in interpretation. This is why the same number may be viewed differently depending on the patient’s age and the local lab method.
The main point is that the anion gap should not be interpreted in isolation. A result that looks abnormal by adult standards may still fit the child’s clinical picture, especially if the rest of the evaluation is reassuring. Conversely, a value within the expected range does not always exclude a important problem if symptoms and other tests suggest otherwise.
Why Anion Gap Values Can Vary in Pediatrics
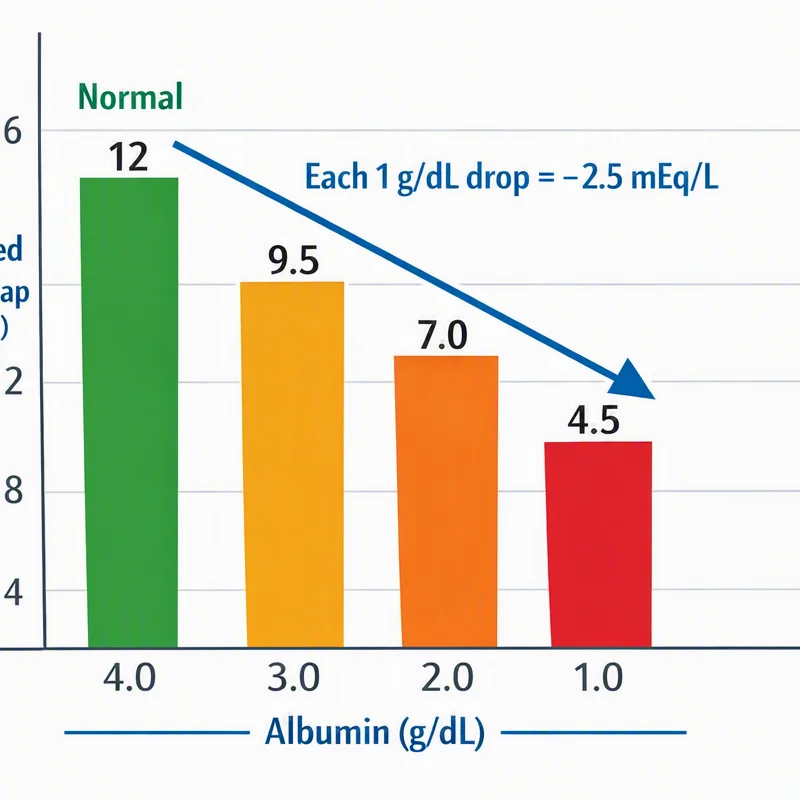
A number of factors may affect the anion gap in children. A key factor is albumin, a negatively charged protein in the blood. Because albumin contributes to the overall charge balance, lower levels can reduce the measured gap. For this reason hypoalbuminemia can lead to a deceptively low result even when another disorder is present.
Growth-related changes also matter. As children progress through growth and adolescence, their fluid status, kidney handling of acids and bases, and metabolism can change. These shifts alter acid-base balance and may serum anion gap calculator influence how a result should be read during clinical interpretation. A child with growth spurts, dehydration, or sudden illness may have different laboratory results than a stable outpatient.
Testing methodology is another important reason values vary. Varying analyzers, calibration methods, sample handling practices, and reporting conventions may yield different results for the same sample. That means a reported normal range may differ from one institution to another. When interpreting an anion gap, clinicians should always compare the result to the lab’s stated reference range rather than assuming a universal value.
In addition, serum albumin concentration, the presence of other unmeasured ions, and overall serum electrolytes can influence the final number. In young patients, these factors make context especially important during medical assessment.
Frequent Causes of an Abnormal Anion Gap in Children
An abnormal anion gap in children often points to an underlying metabolic acidosis or another metabolic issue that requires assessment. A high anion gap usually suggests the buildup of acids that are not directly measured on the electrolyte panel. Common causes include lactic acidosis, ketoacidosis, and renal disease.
Lactic acidosis can occur when tissues are not receiving enough oxygen or when the body is under significant stress from infection, poor circulation, or severe illness. In this setting, lactic acid rises and changes the acid-base balance. Ketoacidosis may occur when the body breaks down fat rapidly for energy, leading to the accumulation of ketones. This can be seen in diabetes and sometimes in fasting or other metabolic conditions.
Renal disease can also cause a high anion gap because the kidneys are less able to eliminate acid effectively. When acid builds up, the blood chemistry changes, and the gap may rise. In pediatric care, these causes are evaluated alongside hydration status, glucose, kidney function, and symptoms.
A low anion gap is less common but may occur with hypoalbuminemia, measurement variation, or unusual electrolyte patterns. Because both high anion gap and low anion gap patterns can reflect important disease processes, pediatric interpretation should be careful and methodical.
How to Understand an Anion Gap Result in a Child
Proper interpretation of the anion gap in a child requires clinical background. This value alone does not diagnose a condition. Instead, clinicians review the full picture, including symptoms, the electrolyte test, a blood gas test, and the child’s pH. These data help determine whether there is a true acid-base imbalance and how severe it may be.
As an example, a child with throwing up, abdominal pain, and elevated glucose may need evaluation for ketoacidosis. A child with fever, low blood pressure, and reduced blood flow may need evaluation for lactic acidosis. A child with kidney problems may have altered acid clearance from renal disease. In all cases, the anion gap is one piece of the diagnostic process.
It is also helpful to assess the result with bicarbonate, pH, and any existing blood gas values. A low bicarbonate level with a elevated gap indicates metabolic acidosis, but the full pattern counts rather than any single result. The goal is clinical assessment rather than single number reading.
While using the Anion Gap Calculator, clinicians should check the unit settings, check the listed lab values, and assess whether the result aligns with the rest of the child’s clinical picture. This matters especially in children’s health, where conditions can change quickly.
When a Elevated or Low Anion Gap Calls for Follow-Up
An abnormal result may need additional workup depending on the child’s symptoms and general condition. A high anion gap accompanied by illness, breathing changes, altered mental status, or signs of poor perfusion can suggest a serious metabolic problem that needs immediate evaluation. A low value may also need follow-up if it is surprising, continued, or paired with worrisome findings.
Dehydration can alter blood chemistry and may worsen an acid-base disturbance. In some children, dehydration accompanies vomiting, diarrhea, fever, or poor intake and can contribute to abnormal lab patterns. If the child also has hypoalbuminemia, the gap may appear smaller than expected, which can make interpretation more difficult.
Toxic ingestion is another reason an abnormal gap may need immediate attention. Certain ingestions can produce a high gap metabolic acidosis, and the child may need urgent testing and treatment. In these situations, the anion gap is often only one clue among many and should be interpreted with history, exam, and additional laboratory tests.
Follow-up is especially important when the result does not fit the clinical picture, when symptoms are worsening, or when there is concern for a serious underlying illness. The more abnormal the value, the more strongly clinicians should consider a full clinical assessment.
Constraints of the Anion Gap in Pediatric Testing
While helpful, the anion gap has important limitations. The first limitation is the reference range itself. Because the normal interval may differ by laboratory and age group, a value should always be interpreted according to the reporting facility’s standards. This is especially relevant in pediatrics, where the same number may not carry the same meaning across all settings.
Analytical error can also affect the result. Slight variations in sodium, chloride, or bicarbonate can change the calculated gap. Since the gap calculation formula depends on these measured values, any inaccuracy in the underlying electrolyte data can alter the final number. Specimen handling, analyzer calibration, and reporting practices all play a role in testing methodology.
A further limitation is that a normal gap does not rule out disease. Some conditions may not produce a clearly elevated gap early on, and mixed disorders can mask one another. Likewise, a low result may be driven by low albumin rather than a primary metabolic problem. This is why clinicians use the anion gap as part of a broader diagnostic approach rather than as a single decisive marker.
In short, the anion gap is a helpful tool, but it has diagnostic limitations. The best use of an Anion Gap Calculator is to guide thoughtful interpretation of pediatric laboratory data, not to replace clinical judgment.
FAQ: Pediatric Anion Gap Questions
Can pediatric patients have different anion gap ranges than adults?
Absolutely. Children can have different expected values depending on age, the laboratory’s reference range, and the testing method used. Younger patients and teens should be interpreted using age-aware medical interpretation when available, rather than assuming adult reference values always apply.
What is a normal anion gap interval in children?
The normal range can vary by lab and by age category, so there is not one universal number for all children. It is best to use the local normal interval provided with the lab tests. A clinician may also review a pediatric reference range when assessing the result in the context of the child’s age and condition.
Why might a child have a high anion gap?
A child may have a elevated anion gap because of metabolic acidosis from causes such as lactic acidosis, ketone-related acidosis, or kidney problems. Other serious illnesses can also affect the gap. The result should be considered alongside symptoms, blood gas findings, and the rest of the electrolyte panel.
Can low albumin affect the anion gap in pediatrics?
Yes. Albumin is an important contributor to the blood’s charge balance, so hypoalbuminemia can lower the measured anion gap. This may make the result look less abnormal than it really is. In pediatric care, low albumin should be considered during pediatric interpretation of the lab result.
When should an abnormal anion gap in a child be evaluated further?
An abnormal result should be evaluated further when it is paired with symptoms, a concerning blood gas result, abnormal pH, signs of illness, or suspicion for a serious metabolic problem. Immediate evaluation may be needed for dehydration, toxic ingestion, severe acidosis, or other unstable findings. A full clinical evaluation helps determine whether the lab pattern reflects a true medical problem.