What Is the Anion Gap?
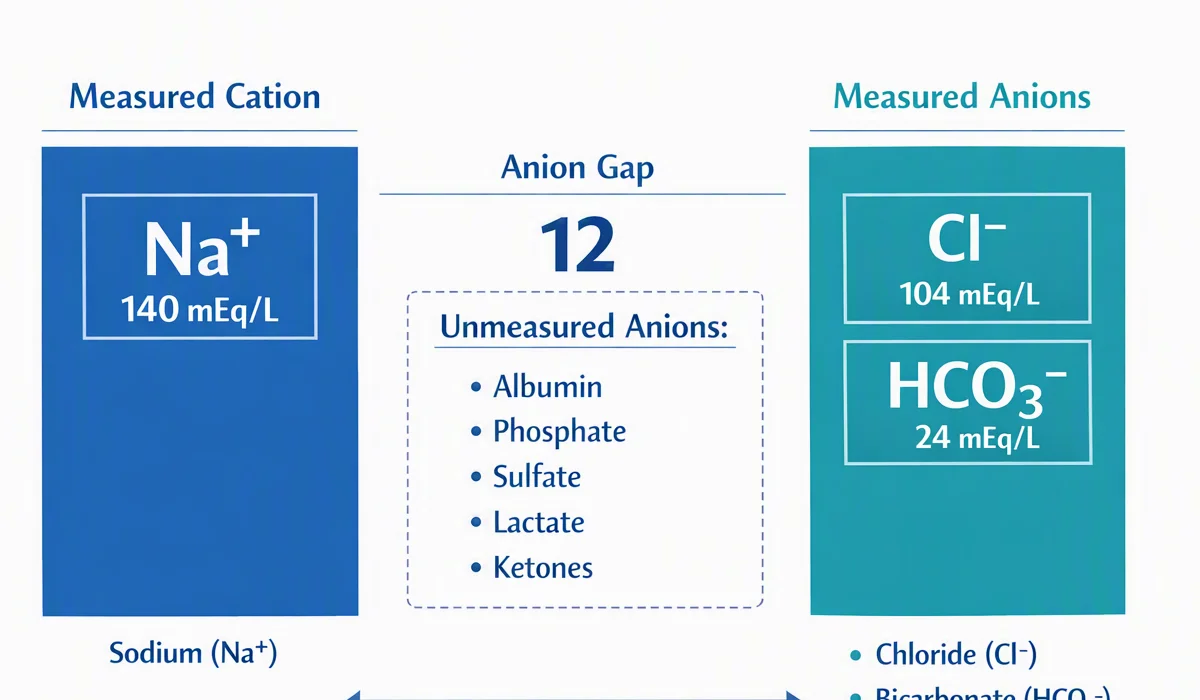
The anion gap is a lab calculation that helps clinicians think about acid-base balance and whether there may be an undetected acid in the blood. It comes from routine electrolytes osmolar gap anion gap comparison measured on routine chemistry tests, especially sodium and chloride, along with bicarbonate. Because the body must keep ion balance in the bloodstream, changes in these values can reveal hidden problems in blood chemistry.
In simple terms, the anion gap is a way to look for a metabolic derangement. A high anion gap suggests additional acids in the blood, while a normal anion gap can still occur in certain acid-base disorders but usually points to a different cause. This is why the anion gap is useful in lab interpretation: it helps identify the cause of systemic acidosis and guides further diagnostic testing.
One important detail is albumin. Since albumin is a protein with a negative charge, low albumin can make the anion gap appear reduced than it really is. That means the raw number is useful, but the clinical context matters. A complete interpretation considers the full serum chemistry picture, including kidney status, glucose, bicarbonate, and other electrolytes.
The way an Anion Gap Calculator Functions
An Anion Gap Calculator is a simple tool that estimates the gap from laboratory values. Many calculators use the same fundamental formula: sodium minus the sum of chloride and serum bicarbonate. Some versions also account for albumin, because albumin affects the reference baseline. The calculator does not diagnose the cause by itself, but it is a practical entry point for spotting anion gap elevation.
These tools are useful because they translate numbers into clinical meaning. If bicarbonate is low, the calculator may show a gap that suggests acids are being added to the bloodstream. If chloride is relatively high and the gap stays normal, that may point more toward a normal anion gap pattern rather than a high-gap disorder. In other words, the calculator helps clinicians distinguish acid-base patterns before deciding on the next steps.
Common inputs include sodium, chloride, bicarbonate, and sometimes albumin. The result is then interpreted with the rest of the serum chemistry panel, symptoms, and other tests. Because the calculation is only one piece of the picture, it should be paired with blood gas testing and a full review of the patient’s history when there is concern for an acidotic state.
Can Diabetes Trigger a High Anion Gap?
Indeed. Diabetes can cause a high anion gap, chiefly when it progresses to diabetic ketoacidosis. Under these conditions, the body is unable to use glucose effectively because of insulin deficiency, so it begins metabolizing fat. That process produces ketones, which are acidity-producing. As ketones build up, they create metabolic acidosis and increase the anion gap.
That is why diabetes is closely linked to ketoacidosis. The gap is not high because of glucose alone; it becomes high because the body is creating organic acids. The primary of these is beta-hydroxybutyrate, which is often the predominant ketone in diabetic ketoacidosis. As ketone production rises, bicarbonate is consumed while buffering the acid, and the lab pattern shifts toward a increased-gap metabolic acidosis.
It is also important to understand what diabetes does not automatically do. Many people with diabetes and high glucose do not have a high anion gap. The elevation happens when there is a genuine acid load, especially from ketones or another cause of acidosis. That is why the question is not simply “Does diabetes raise the anion gap?” but rather “Has diabetes caused an acid-base disorder that leads to anion gap elevation?”
Diabetic ketoacidosis as the Main Cause
Diabetic ketoacidosis is the typical diabetes-related reason for a high anion gap. In this condition, insulin deficiency prevents normal glucose use, so the body turns to fat breakdown. Fat metabolism increases ketone production, especially beta-hydroxybutyrate, which contributes to metabolic acidosis.
As ketones build up, they function as organic acids and lower bicarbonate. The result is an acidotic state with a widened anion gap. This can happen fast and often comes with dehydration, vomiting, and marked glucose abnormalities. The presence of ketones in blood or urine supports the diagnosis, but blood beta-hydroxybutyrate is often the most accurate marker for the severity of ketoacidosis.
In simple terms, diabetic ketoacidosis is a treatment-urgent condition because it indicates a critical shift in metabolism. The high anion gap is not the disease itself; it is a indicator that the body is failing to maintain normal acid-base balance.
Other Diabetes-Related Causes of Elevated Anion Gap
Although diabetic ketoacidosis is the primary explanation, other diabetes-related problems can also lead to an elevated anion gap. One example is lactic acidosis, which can occur when tissues do not get enough oxygen or when severe illness interferes with normal metabolism. Diabetes can contribute indirectly through poor perfusion, infection, or other complications.
Kidney failure is another key issue. When renal function declines, the body cannot clear acids effectively, and metabolic waste products accumulate. This can produce a high anion gap even if ketones are not the primary issue. Diabetes is a common cause of chronic kidney disease, so the link matters in practical lab interpretation.
Hyperglycemia and dehydration often occur together in uncontrolled diabetes. While high blood sugar alone does not always raise the anion gap, severe dehydration can impair circulation, impair kidney function, and contribute to lactic acidosis or ketoacidosis. So diabetes may establish the conditions for a high-gap picture even when ketones are not the only factor.
What Symptoms Point to a Severe High Anion Gap?
A dangerous high anion gap often comes with clear clinical signs. One of the key is Kussmaul breathing, a deep and rapid breathing pattern that shows the body’s attempt at respiratory compensation for metabolic acidosis. This pattern is particularly alarming when it appears with dehydration or confusion.
Other alerting symptoms include nausea, vomiting, abdominal pain, weakness, and signs of worsening illness. As the acid-base problem becomes more severe, a person may develop altered mental status, ranging from confusion to lethargy. These symptoms suggest the body is struggling to preserve normal function during a significant metabolic derangement.
When symptoms are paired with diabetes, high glucose, and a high anion gap, the concern for ketoacidosis rises quickly. Because the condition can progress quickly, treatment urgency matters. Any combination of deep breathing, vomiting, dehydration, and confusion should be taken with urgency.
In What Way Doctors Establish What Is Causing It
To establish the cause of a high anion gap, doctors combine several studies instead of relying on one result. A basic metabolic panel is often the initial test because it shows sodium, chloride, bicarbonate, and glucose. These values help reveal the pattern and estimate the severity of the acid-base disorder.
A blood gas is then performed to assess pH and the degree of acidosis. It helps indicate whether the body is in a true acidotic state and whether there is adequate respiratory compensation. Because the anion gap is only one part of the picture, a blood gas adds key context for diagnosing systemic acidosis.
Doctors also check glucose and perform a ketone test, especially if diabetes is known or suspected. Blood ketone testing is often favored because it can detect beta-hydroxybutyrate more directly. Together, the glucose level, ketones, and basic metabolic panel help distinguish diabetic ketoacidosis from other causes such as lactic acidosis or kidney failure.
Albumin may also be reviewed to interpret the gap correctly. A low albumin level can mask an elevated gap, so clinicians may adjust the calculation or interpret the result carefully. Here, thoughtful lab interpretation and diagnostic testing work together.
When a High Anion Gap Is an Emergency
A high anion gap becomes an emergency when it reflects significant acidemia, symptoms that worsen quickly, or suspected diabetic ketoacidosis. This is the point where emergency care is required because the body may be unable to compensate further. A dangerous acid load can affect respiration, the cardiovascular system, and brain function.
Common emergency treatments include fluid replacement and insulin therapy, especially if diabetic ketoacidosis is the cause. Fluids help restore fluid balance and improve perfusion, while insulin decreases glucose levels and stops ketone production. As ketones drop and bicarbonate returns, the anion gap can begin to close.
Severe acidosis is not something to watch at home. A person with Kussmaul breathing, vomiting, confusion, or very high glucose needs prompt medical evaluation. The goal is not just to lower the number on the calculator but to treat the metabolic emergency before it causes greater complications.
Common Questions On Diabetes & High Anion Gap
Does diabetes cause a high anion gap?
Absolutely. Diabetes can lead to a high anion gap, usually through diabetic ketoacidosis. In such cases, insulin deficiency leads to ketones, especially beta-hydroxybutyrate, which trigger metabolic acidosis and increase the anion gap.
Will diabetic ketoacidosis always lead to a high anion gap?
Typically, yes, because diabetic ketoacidosis generates acid from ketones and decreases serum bicarbonate. However, lab patterns can vary depending on timing, treatment, and other factors, so clinicians look at blood gas results, ketone test findings, and the basic metabolic panel together.
May high blood sugar raise the anion gap without ketoacidosis?
High blood sugar alone does not automatically increase the anion gap. The gap usually goes up when hyperglycemia is part of a larger metabolic acidosis, such as ketoacidosis, lactic acidosis, or kidney failure. That is why glucose must be assessed with electrolytes, ketones, and clinical signs.
Which is the normal anion gap range?
The anion gap normal range depends on the laboratory and the formula used, including whether albumin is considered. Many labs use a range that is roughly around 8 to 12 mEq/L, but reference intervals vary. The most important step is to compare the result with the specific lab’s reference range.
At what point should a high anion gap be considered an emergency?
A high anion gap should be considered an emergency when it is paired with severe acidosis, deep or rapid breathing, vomiting, confusion, dehydration, or suspected diabetic ketoacidosis. In those situations, emergency care is needed right away because the cause may require fluid replacement, insulin therapy, and close monitoring.