Defining the Anion Gap?
The anion gap is a calculated value used to help interpret acid-base disorders and spot abnormal shifts in serum electrolytes. It is usually derived from common lab data on a basic metabolic panel and is based on the main measured ions: sodium, chloride, and bicarbonate.
At a practical level, the anion gap reflects the difference between positive and negatively charged components in blood. Because many ions are not directly measured on standard tests, the calculation helps clinicians infer whether extra acids or other unmeasured ions may be present. This makes it helpful in the evaluation of metabolic acidosis and broader acid-base balance.
In basic form, the anion gap calculation compares sodium against chloride and bicarbonate. A increased result may suggest a build-up of acids, while a low or normal result does not always mean the body is free of metabolic derangement. That is why clinical interpretation matters as much as the number itself. An Anion Gap Calculator can speed up the arithmetic, but it cannot take the place of medical assessment of the underlying pathophysiology.
How Albumin Influences the Anion Gap
Albumin is the most common protein in plasma and one of the most important negatively charged proteins in the bloodstream. Because of its charge, albumin plays a major role in the pool of unmeasured anions that help determine the expected anion gap. In other words, part of the “missing” charge in the formula is normally supplied by serum protein, especially albumin.
When serum albumin concentration drops, the body has fewer negatively charged particles contributing to the expected baseline. That means the measured anion gap may appear lower than it truly should be, even if an acid load is present. This is where protein binding and unmeasured electrolytes become important to clinical interpretation.
The relationship is direct: lower albumin tends to reduce the observed anion gap, while higher albumin can raise it. Since the standard reference interval assumes typical albumin levels, any major deviation can alter the result. That distortion can obscure the true state of the patient’s acid-base status and hide a meaningful gap.
Why Albumin Adjustment Is Necessary
Hypoalbuminemia is a frequent reason the anion gap becomes inaccurate. When albumin is low, the measured value may drop into the normal range even when unmeasured acids are building up. This is why clinicians often calculate a corrected anion gap rather than counting only on the original result.
Albumin correction enhances acid-base interpretation by accounting for a major variable that changes the baseline. Without this adjustment, a patient with true high anion gap metabolic acidosis may be misclassified as having a normal gap disorder or no gap disorder at all. That can slow recognition of serious disease.
The goal is clinical accuracy. A corrected result helps show whether there is a hidden increase in unmeasured anions. This matters because the difference between a normal laboratory values pattern and a true elevated gap can change the entire diagnostic pathway, especially in acute illness.
How to Correct the Anion Gap for Albumin
The formula for albumin correction adjusts the measured anion gap based on the patient’s serum albumin. The concept is clear: because albumin contributes to the normal gap, each decline in albumin requires a corresponding increase in the interpreted result. Many clinicians use a correction factor tied to the difference from the usual expected range.
A commonly used approach adds a set amount to the anion gap for every drop in albumin below normal. The exact formula may differ by institution, but the purpose is the same: adjust the gap to what it would likely be if albumin were normal. This is where an anion gap calculator can be especially useful, because it can complete the anion gap calculation and apply the albumin adjustment rapidly.
In practice, the clinician inputs the measured sodium, chloride, bicarbonate, and serum albumin. The calculator then calculates the corrected value, helping minimize errors in bedside interpretation. This process improves better medical assessment, especially when a low albumin level might otherwise hide clinically important abnormalities.
When a Normal Anion Gap Can Be Misleading
A regular gap does not always mean there is no significant acid problem. In fact, acid-base acidosis may still be present even when the anion gap appears unchanged if albumin is decreased. This can create hidden acidosis, where the expected rise in gap is blunted by hypoalbuminemia.
This issue is notably important in patients with lactic acidosis or ketoacidosis. Both conditions can produce a true rise in unmeasured acids, but the gap may look deceptively ordinary if albumin is depressed. In those cases, the corrected anion gap may reveal an unrecognized high anion gap acidosis that would otherwise be missed.
That is why clinicians should not stop at the original number. The broader clinical picture matters, including the patient’s symptoms, vital signs, and other lab markers. A simple “normal” result can hide substantial metabolic derangement, especially if the underlying process is progressing fast or mixed with other disorders.
Common Causes of Reduced Albumin
A number of conditions can reduce albumin and as a result skew the anion gap. Liver disease may impair albumin synthesis, causing lower circulating levels over time. Because the liver synthesizes albumin, chronic hepatic dysfunction often has a direct effect on the serum protein balance that maintains the normal gap.
Nephrotic syndrome can lead to major urinary loss of albumin, which reduces the serum albumin concentration and modifies the expected anion gap. In malnutrition, reduced protein intake and poor overall nutritional status can also cause hypoalbuminemia. These changes may be progressive, but they have major consequences for interpretation of blood chemistry.
Inflammation is an additional common cause. During acute or chronic inflammatory states, albumin often falls as part of the body’s response. Because inflammation is frequent in hospitalized and critically ill patients, albumin correction is often crucial for accurate clinical interpretation in real-world settings.
In what way do Clinicians Interpret the Corrected Anion Gap
Clinicians use the corrected anion gap as part of the evaluation for acid-base disorders. It is not used in isolation; rather, it is paired with history, physical findings, and test results such as the arterial blood gas and basic metabolic panel. Together, these data help clarify whether a patient has an elevated gap, a normal gap, or a mixed process.
The corrected result can change clinical decision-making in important ways. For example, if the uncorrected gap looks normal but the corrected value is elevated, the clinician may look more closely for toxins, tissue hypoperfusion, renal dysfunction, or other causes of acid buildup. This is especially useful when the patient appears ill but the standard numbers seem reassuring.
Albumin correction also supports better recognition of compensatory changes. A patient may show partial compensation on blood gas testing, and the corrected gap helps determine whether the compensation is appropriate or whether another hidden disorder is present. This improves diagnostic accuracy and helps clinicians avoid premature closure.
Constraints and Pitfalls of Albumin Correction
While albumin correction refines interpretation, it is not perfect. Laboratory variation can affect sodium, chloride, bicarbonate, and albumin measurement, which means slight variations between labs may affect the calculated result. This is one reason the corrected anion gap should always be interpreted in context.
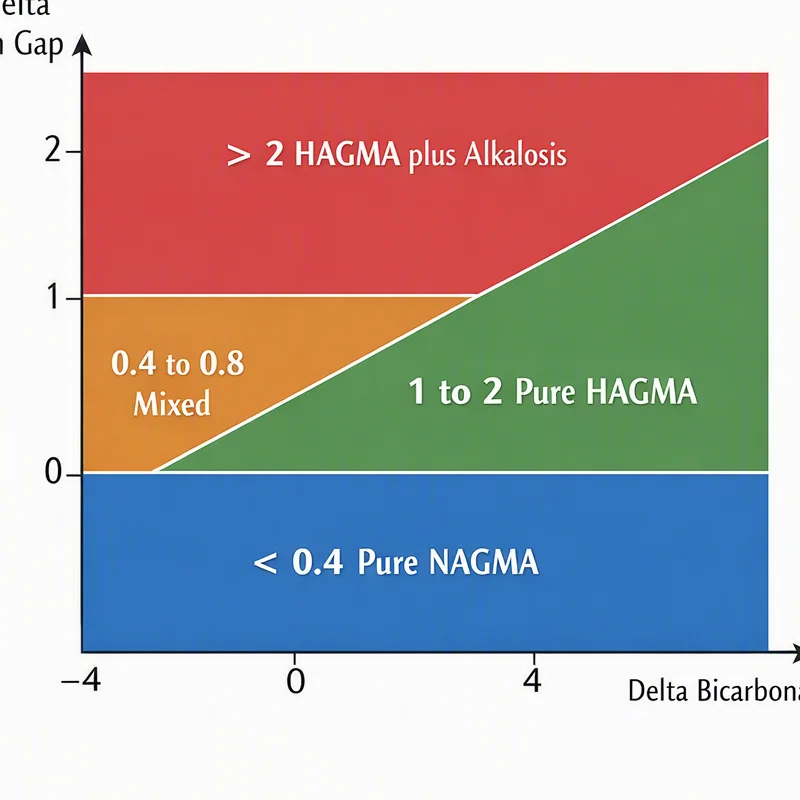
Another issue is the mixed acid-base disorder. A patient may have more than one process occurring at once, such as lactic acidosis along with vomiting-related alkalosis or renal compensation. In these situations, the corrected gap may suggest a hidden acidosis, but it may not fully explain the entire pattern. Additional tools like the delta gap can help identify whether the rise in gap matches the fall in bicarbonate.
There are also broader diagnostic limitations. The albumin correction formula is an estimate, not a direct measurement of all unmeasured ions. Other abnormalities in protein binding, anion gap calculator with potassium inorganic ions, or the patient’s overall metabolic state may influence the result. For that reason, clinicians should use the corrected number as one piece of the full acid-base evaluation, not as the sole answer.
FAQs About albumin correction and the Anion Gap
Why does low albumin lower the anion gap?
Low albumin decreases the anion gap because albumin normally provides a large share of the blood’s unmeasured anions. When albumin falls, there are fewer negatively charged particles in the serum, so the calculated gap decreases even if the true acid-base status has not improved. This is why hypoalbuminemia can make the anion gap look deceptively normal.
How is the anion gap corrected for albumin?
You use an albumin correction formula that adjusts the measured anion gap based on the patient’s serum albumin. In practice, the correction adds a set amount for each unit that albumin falls below the usual reference range. An anion gap calculator can automate the arithmetic, but the clinician still needs to interpret the corrected number in the context of the patient’s overall condition.
When should albumin adjustment be applied?
Albumin correction should be applied whenever albumin is low or possibly low, most notably in patients with metabolic acidosis, suspected high anion gap metabolic acidosis, or unclear acid-base findings. It is especially helpful when evaluating critically ill patients, because hypoalbuminemia is often present and can conceal a true increase in acid burden.
Can a normal anion gap hide a serious acidosis?
Certainly. A normal anion gap can conceal serious acidosis when low albumin masks the increase in unmeasured anions. This can occur with lactic acidosis, ketoacidosis, and other sources of occult high anion gap acidosis. A corrected value often reveals the hidden process and enhances acid-base balance assessment.
Is an anion gap calculator enough without albumin correction?
No, it is not. An anion gap calculator is helpful for the initial calculation, but without albumin correction it may miss important abnormalities in patients with low albumin. For accurate clinical interpretation, the calculator should include or be followed by albumin adjustment. That approach improves diagnostic accuracy and helps clinicians avoid overlooking hidden acid-base disorders.