Understanding the Anion Gap?
The anion gap is a calculated anion gap clinical significance value that helps clinicians assess electrolytes in the blood and gain insight into acid-base balance. It is not a directly measured lab result. Instead, it is calculated from common serum chemistry values, especially sodium, bicarbonate, and chloride. Because the calculation compares measured cations and measured anions, it can reveal the presence of unmeasured anions that may not be obvious on a routine blood test.
At a simple level, the anion gap is helpful because blood must remain electrically balanced. That balance reflects the principle of electroneutrality, meaning the total positive and negative charges in plasma should be approximately equal. Since not all ions are directly measured in standard blood chemistry, the anion gap offers a practical estimate of the difference between measured ions and the ions left out of the basic panel.
The value is commonly reviewed as part of a routine electrolyte panel or broader blood test. When the number is higher or lower than expected, it can point toward an underlying electrolyte imbalance or metabolic acidosis. That is why the anion gap is often used as a diagnostic marker in evaluating acid-base disorders.
For many people, the phrase “anion gap” sounds complicated, but the idea is easy to grasp: the calculation helps show whether something unusual is affecting the body’s blood chemistry. An Anion Gap Calculator makes this simpler by turning raw lab values into a number that supports clinical interpretation.
What Role Does Chloride Play in the Anion Gap?
Chloride is one of the main measured anions in the blood, and it plays a central role in maintaining electroneutrality. In the anion gap calculation, chloride is part of the measured group that is compared against sodium and bicarbonate. If chloride rises or falls, the anion gap can change even when other values are stable.
This is where the connection becomes important. When the body is losing bicarbonate, chloride frequently rises to preserve charge balance. That response is part of a compensatory mechanism that maintains plasma electrically balanced. In practice, this means changes in the chloride level can alter the anion gap without necessarily signaling the identical condition every time.
Chloride also assists clinicians in evaluating whether the issue is caused by ions not measured or by a shift in measured ions. In certain acid-base disorders, the body may hold on to more unmeasured ions, causing a high anion gap. In other cases, the main change is an increase in chloride, which can leave the anion gap normal even when the person has clinically important acidosis.
This is why chloride is more than just a backup measurement. It is a central element of anion gap interpretation. The very same serum electrolytes can show different stories depending on whether chloride is increased, decreased, or the same. To put it another way, chloride helps differentiate between patterns that reflect a real buildup of acids and profiles that reflect a variation in measured ions.
From a practical standpoint, chloride’s place within the serum chemistry profile plays a key role in standard chemistry review. A clinician may look at the chloride result together with sodium and bicarbonate to assess if the pattern suggests metabolic acidosis, volume changes, renal issues, or a different reason for abnormal lab findings.
Formula for the Anion Gap and How Chloride Affects the Result
The classic anion gap formula is often written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Since chloride appears within the parentheses, any shift in chloride directly changes the final value. If chloride increases while sodium and bicarbonate stay the same, the calculated anion gap decreases. If chloride decreases, the anion gap increases. This is why even small shifts in chloride can matter during diagnostic review.
Let’s break down the logic in simple terms. Sodium is the primary measured cation in the calculation. Chloride and bicarbonate are the principal measured anions. The formula estimates the difference between the positive and negative charges that are measured. Any remaining difference reflects the presence of unmeasured ions such as organic acids, proteins, and other contributors to blood chemistry.
Because bicarbonate is a major buffer in the body, it frequently changes during acid-base disorders. When plasma bicarbonate drops, chloride may rise to preserve balance. This is part of the body’s buffer system and can create a normal anion gap pattern even when acidosis is present. Understanding this relationship is essential for accurate anion gap interpretation.
Here is the basic idea:
- A higher chloride level usually lowers the calculated anion gap. Decreased chloride typically raises the calculated anion gap. Bicarbonate changes often produce predictable chloride shifts. The result should always be reviewed with the full electrolyte panel and the clinical picture.
The equation is basic, but the meaning behind it is not always obvious. That is why an Anion Gap Calculator can be useful for rapidly converting lab values into a useful result, especially when reviewing multiple serum electrolytes at once.
Standard Anion Gap vs Increased Anion Gap vs Low Anion Gap
A regular anion gap usually means the relationship between measured cations and measured anions is inside the expected expected range. This does not necessarily mean everything is fine, though. A person can still have non-anion gap metabolic acidosis or another pH balance problem even when the anion gap is not high.
A increased anion gap metabolic acidosis implies there are additional not measured anions in the blood. Common examples include acids that build up during illness or impaired metabolism. When this happens, bicarbonate is often consumed as it buffers acid, and the gap rises because the formula is no longer balanced by the expected measured ions.
A decreased anion gap is less common but can be medically significant. It may occur when chloride is relatively high, sodium is decreased, bicarbonate levels are increased, or when albumin is reduced. Albumin matters since it is a key unmeasured anion in plasma. If albumin drops, the measured gap can decrease even if the person has another problem that should not be missed.
In actual use, clinicians do not read the number in isolation. They consider the full profile of electrolytes, the patient’s complaints, and related serum chemistry findings. A Article source normal result can still be significant if it fits a pattern such as hyperchloremia, and a low result may suggest an issue with albumin or laboratory measurement.
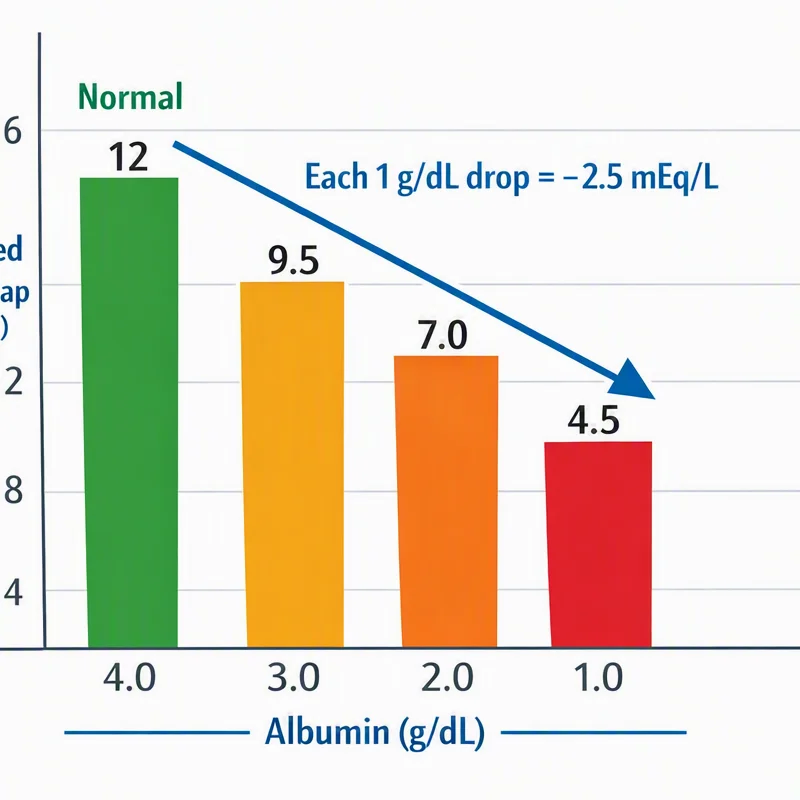
These classifications help structure thinking:
- Normal anion gap: commonly seen when chloride rises to compensate for bicarbonate loss. High anion gap metabolic acidosis: often reflects extra acids or unmeasured anions. Low anion gap: may appear with low albumin, increased chloride, or other contributors.
So, the anion gap is not only a measurement. It is a pattern that helps relate blood chemistry to the likely cause of the abnormality.
Why Chloride Increases When the Anion Gap Is Normal
A key one of the most important interpretation patterns is the link between hyperchloremia and a normal anion gap. When bicarbonate is depleted from the body, chloride often increases to maintain electroneutrality. The result is non-anion gap metabolic acidosis, also called hyperchloremic metabolic acidosis.
This presentation appears because the body trades lost bicarbonate with chloride. Consequently, the sum in the anion gap formula stays relatively stable. The acid-base disturbance is real, but the gap does not rise because there is not a large accumulation of unmeasured anions. Instead, the main issue is a shift in measured ions.
A frequent cause for this is bicarbonate loss. When bicarbonate is lost through the gastrointestinal tract or the kidneys, chloride helps fill the gap left behind. That is why patients with diarrhea may develop a normal anion gap metabolic acidosis. The same pattern can happen in renal tubular acidosis, where the kidneys fail to handle acid or bicarbonate properly.
These cases matter because a normal anion gap does not mean “no acidosis.” It means the problem may be due to chloride replacement rather than an increase in unmeasured acids. Recognizing this distinction is central to understanding anion gap interpretation.
In simple terms:
- Bicarbonate falls. Chloride increases. The gap stays within normal limits. The person may still have metabolic acidosis.
That pattern is one reason chloride is so clinically useful. A rising chloride level can be a clue that the body is responding to bicarbonate loss rather than accumulating acid from another source.
How an Anion Gap Calculator Is Used in Clinical Interpretation
An Anion Gap Calculator helps change raw lab values into a result that can be reviewed quickly and uniformly. Clinicians often use it after checking a basic electrolyte panel because the result helps organize the next step in assessment. When paired with the full clinical picture, it supports assessment of acid-base balance and possible causes of abnormal serum electrolytes.
The calculator is especially useful when a blood test shows changes in sodium, chloride, or bicarbonate. By placing those measurements into the formula, the calculator helps determine whether the pattern suggests a normal anion gap, high anion gap metabolic acidosis, or low anion gap pattern. That can inform further review of renal function, fluid status, and possible acid-base disorders.
In clinical interpretation, the calculator is not the final answer. It is a initial reference. The result should be viewed alongside the patient’s symptoms, renal function, and any signs of infection, dehydration, or toxin exposure. It may also be adjusted for albumin when needed, since albumin strongly alters the measured value.
A few practical ways clinicians think about it:
- Does the result suggest extra unmeasured ions? Is chloride increased, suggesting hyperchloremia? Is bicarbonate decreased, pointing toward metabolic acidosis? Does the pattern match the patient’s acid-base balance?
Because the anion gap is a calculation rather than a direct test, the context matters. The same serum chemistry values can have different meanings depending on the trend, the symptoms, and the likely cause. That is the value of an Anion Gap Calculator: it supports faster and clearer interpretation of a common but nuanced lab result.
Frequent Reasons of Abnormal Chloride and Anion Gap Values
Multiple conditions can alter chloride and modify the anion gap. Many of the most common include dehydration, kidney disease, diarrhea, and lactic acidosis. Every one changes blood chemistry in different ways, so the chloride pattern helps narrow the explanation.
Dehydration can make more concentrated serum electrolytes and sometimes cause increased chloride levels. In some cases, volume loss also changes sodium and bicarbonate, making the overall picture more complex. Reviewing the full electrolyte panel is essential rather than focusing on a single value.
Kidney disease can impair the body’s ability to manage acid, sodium, chloride, and bicarbonate. When the kidneys cannot process these ions well, the result may be a high or normal anion gap depending on the cause. Changes in renal function can also alter how the body maintains acid-base balance.
Diarrhea commonly causes loss of bicarbonate from the gastrointestinal tract. Because chloride often increases to preserve electroneutrality, this may produce non-anion gap metabolic acidosis. The pattern is often accompanied by hyperchloremia and a lower bicarbonate level.
Lactic acidosis is a classic cause of high anion gap metabolic acidosis. In this case, extra organic acids increase the gap because they represent additional unmeasured anions. Chloride may not be the primary driver of the change, but its relationship to bicarbonate still matters when interpreting the result.
Hypochloremia can also be notable. Low chloride may increase the anion gap even if the person does not have a major buildup of unmeasured acids. This can happen with vomiting, certain medications, or metabolic alkalosis patterns. Again, the key is to consider the chloride level as part of the overall blood chemistry picture.
In short, abnormal chloride and anion gap values should be considered as indicators. They do not diagnose a condition on their own, but they help determine the likely direction of the problem and whether the issue involves bicarbonate loss, acid accumulation, or another type of electrolyte imbalance.
FAQ About chloride and the Anion Gap
What’s the role of chloride in the anion gap?
Chloride is one of the main quantified anions used in the anion gap formula. It helps determine whether the blood has a normal balance of measured ions or whether there may be extra unmeasured anions. Because chloride is included directly in the calculation, changes in chloride can raise the anion gap and affect anion gap interpretation.
Why does chloride rise when bicarbonate falls?
When bicarbonate drops, the body often raises chloride to preserve electroneutrality. This is a compensatory mechanism that keeps the electrical balance of the blood steady. The pattern is common in non-anion gap metabolic acidosis, where bicarbonate loss is replaced by chloride rather than by extra acids.
Could a normal anion gap still indicate a problem with chloride?
Yes. A normal anion gap can still occur with clinically important chloride abnormalities, especially hyperchloremia or hypochloremia. In these cases, the anion gap may not be elevated even though the person has an acid-base disorder. That is why the full electrolyte panel and clinical context are essential.
What does a high chloride level mean in an anion gap test?
A high chloride level often suggests that chloride is replacing lost bicarbonate or that there is another type of electrolyte imbalance affecting blood chemistry. It may be seen in non-anion gap metabolic acidosis, including cases related to diarrhea or renal tubular acidosis. The meaning depends on the rest of the lab values and the full clinical picture.
How can an Anion Gap Calculator help interpret lab results?
An Anion Gap Calculator converts sodium, chloride, and bicarbonate results into a calculated value that supports faster review of blood test findings. It helps clinicians and patients see whether the pattern suggests a normal anion gap, high anion gap metabolic acidosis, or low anion gap. Used correctly, it improves understanding of acid-base balance and highlights when further evaluation may be needed.