What is the anion gap and what makes it useful in ICU?
The anion gap is a practical way to interpret acid-base balance using a routine electrolyte panel. It examines the major measured cations and anions, mainly sodium, chloride, and bicarbonate, to estimate the amount of unmeasured anions in serum. In the ICU, this is significant because a rising or falling anion gap can be an early clue to a significant metabolic derangement before the patient’s condition becomes obvious clinically.
For critically ill patients, the anion gap is not just a number. It is a signal that helps direct the diagnostic approach to metabolic acidosis and other acid-base disorders. It can point toward high anion gap metabolic acidosis, identify hidden acid loads, and reveal a compensatory response that is not yet complete. Because ICU patients often have overlapping problems such as shock, kidney injury, infection, and fluid shifts, the anion gap is best interpreted in clinical context, not in isolation.
Changes in chloride and bicarbonate can also reflect a chloride shift or iatrogenic fluid effects. For example, hyperchloremia may lower the anion gap, while hypochloremia may make the gap appear elevated relative to the patient’s actual acid burden. That is why the anion gap is a beginning point for interpretation, not the final answer.
How can you calculate the anion gap?
The classic anion gap calculation uses the measured serum concentrations of sodium, chloride, and bicarbonate:
Anion gap = sodium − (chloride + bicarbonate)
Many clinicians use an anion gap calculator to make this step faster and limit calculation mistakes, especially when caring for several patients or reviewing serial labs during sudden clinical changes. It can be very useful, but it only works well if the input values are accurate and the result is interpreted alongside the rest of the data.
Lab methods and reference intervals can vary a bit between institutions, so the numeric result should always be compared with the local reference range. Some clinicians also include potassium in the formula, but the sodium-based version is most commonly used in ICU practice. What matters is that the gap represents the relationship between measured electrolytes and the presence of additional acid anions such as lactate, ketones, or toxic metabolites.
As it is calculated from the basic chemistry panel, it can be repeated easily over time. That makes it valuable for tracking trends, assessing response to therapy, and watching for evolving acid-base disorder patterns. In ICU care, repeated labs often matter more than one isolated value.
What’s a typical anion gap in critically ill patients?
A “normal” anion gap depends on the lab method, the hospital, and the patient’s albumin status. The local reference range may vary from what clinicians recall from training, so the printed lab interval should guide interpretation. In general, an anion gap within the reference range suggests that the major unmeasured acids are not significantly raised, but that does not fully exclude clinically important acidosis.
Albumin has a major effect because it is a negatively charged protein and a key contributor to the expected gap. In critical illness, low serum albumin is frequent, and the measured anion gap may therefore seem falsely low. For that reason, the albumin-corrected anion gap is often more informative than the uncorrected value.
When the albumin level is reduced, a “normal” gap may actually represent a masked rise relative to the patient’s baseline. This matters because clinicians may otherwise miss a substantial acid excess. The result should be viewed as part of the full acid-base balance assessment, including pH, bicarbonate, respiratory compensation, and the broader clinical context.
What triggers an elevated anion gap in intensive care?
A high gap usually suggests excess unmeasured anions from metabolic or inorganic acids. In the ICU, frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each condition has a distinct pathophysiology, but all raise the gap by introducing acid anions that are not directly measured on the standard chemistry panel.
Lactic acidosis is one of the most frequent causes in severely ill patients. It may result from shock, sepsis, hypoperfusion, hypoxemia, seizures, beta-agonist exposure, or impaired lactate clearance. Because lactate can rise quickly, it is often a key target in the early diagnostic approach. A rising gap with lactate elevation strongly points to tissue hypoperfusion or another major metabolic stressor.
Ketoacidosis may occur in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. Here, ketone bodies are the unmeasured anions driving the gap. Checking ketones is essential if the clinical picture includes hyperglycemia, poor intake, vomiting, or altered mental status.
Renal failure can also produce a high gap because the kidneys cannot excrete acid effectively. Retained sulfate, phosphate, urate, and other organic acids accumulate, creating a pattern of high anion gap metabolic acidosis. In advanced kidney injury, the acid burden may be substantial even before creatinine peaks, so the anion gap can serve as an earlier clue.
Toxic alcohols such as methanol, ethylene glycol, and related substances can produce severe metabolic acidosis with an elevated gap. This diagnosis is sensitive to timing. The gap may be an early trigger to broaden the differential and evaluate osmolar status, neurologic findings, and exposure history.
In all of these situations, the size of the gap does not tell the whole story. Severe illness can coexist with a modest gap, and a very high gap can develop rapidly. Trend the result and compare it with the patient’s symptoms, hemodynamics, and other laboratory data.
What causes a normal anion gap metabolic acidosis?
A normal anion gap metabolic acidosis is also called hyperchloremic acidosis because the fall in bicarbonate is often balanced by a increase in chloride, maintaining the gap. Frequent causes are diarrhea, renal tubular acidosis, and large-volume chloride-rich fluid infusion. In these cases, the problem is not a accumulation of unmeasured acids but rather a loss of bicarbonate or a failure to reclaim or generate it effectively.
Diarrhea can cause marked gastrointestinal bicarbonate loss, especially when pronounced or extended. The body responds with a modest increase in chloride, leading to hyperchloremic acidosis. This pattern may be seen in septic patients, after surgery patients, and those with enteral losses.
Renal tubular acidosis includes conditions where the kidneys cannot make acidic urine or retain bicarbonate properly. The result is metabolic acidosis with a normal gap, and the diagnosis often needs urine studies and careful review of the clinical context.
Elevated chloride from IV fluid therapy can also be a factor. Because chloride rises as bicarbonate falls, the gap stays “normal” even while the patient remains acidemic. This is one reason the ICU team should not stop at the anion gap alone when evaluating acid-base disorders.
In what way does hypoalbuminemia alter the interpretation?
Hypoalbuminemia is a major reason the observed anion gap can fool clinicians in the ICU. Since albumin is a primary unmeasured anion, lower levels lower the expected gap. As a result, a patient with marked metabolic acidosis may still show a normal or only mildly elevated measured value.
The usual correction formula modifies the gap upward when albumin is low. Various formulas exist, but the concept is the same: lower albumin means the “baseline” gap should be assumed to be lower, so the observed value must be corrected to avoid downplaying the acid burden. The albumin-corrected anion gap is especially useful in critical illness, where inflammation, capillary leak, malnutrition, liver dysfunction, and dilution can all decrease serum albumin.
Using the corrected value enhances detection of hidden high anion gap metabolic acidosis. It can also prevent false reassurance when the uncorrected number looks acceptable. In practice, if albumin is clearly low, the corrected gap should be assessed alongside the blood gas, lactate, and the rest of the clinical picture.
In ICU interpretation, a normal measured gap with low albumin may not be truly normal.
How should you understand the anion gap with mixed acid-base disorders?
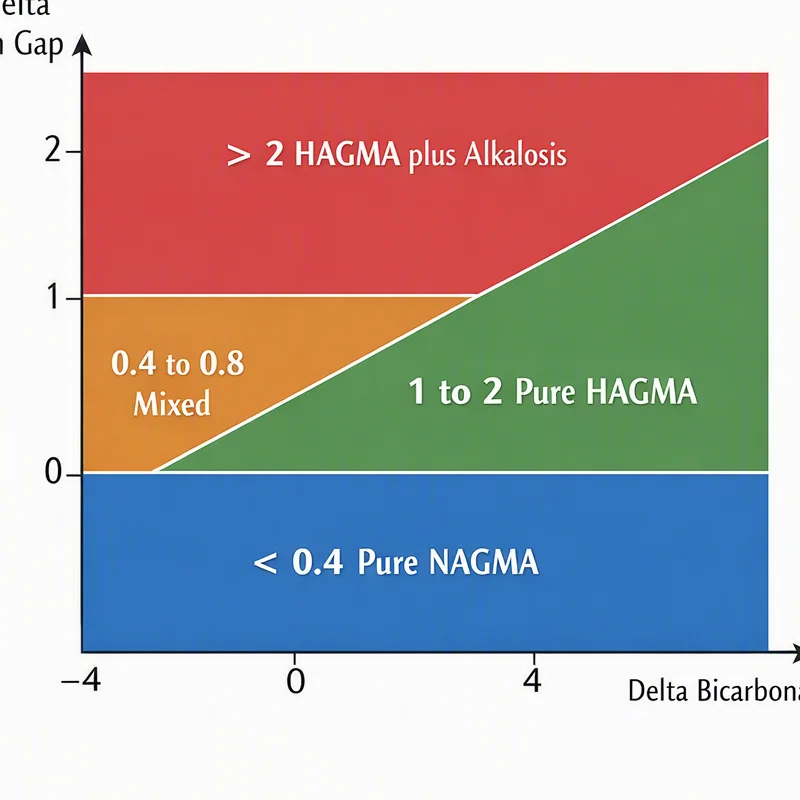
A multiple acid-base disorder is common in very sick patients and can obscure important findings. A patient may have both increased anion gap acidosis and another process such as metabolic alkalosis or normal gap acidosis. The anion gap helps identify the presence of a high-gap process, but the bicarbonate and pH pattern indicate whether something else is also occurring.
The delta gap and delta-delta ratio are useful tools for this evaluation. The delta gap compares the rise in anion gap above normal to the fall in bicarbonate. The delta-delta ratio helps clarify whether the change in bicarbonate is proportionate to the change in gap. If the ratio is abnormal, a second acid-base process may be present.
For example, a patient with lactic acidosis may also have vomiting-related metabolic alkalosis, or a patient with chronic kidney disease may have simultaneous respiratory compensation and hyperchloremia. Mixed disorders are frequent in critical illness because patients often have multiple drivers of acid-base disturbance at once.
The practical point is that a single elevated anion gap clinical significance anion gap should not finish the analysis. Review the blood gas, bicarbonate, chloride, albumin, and clinical course together. The goal is not only to label the disorder but to understand what is driving the patient’s current physiology.
What are the most common ICU pitfalls when working with an anion gap calculator?
A frequent pitfall is laboratory artifact. Blood sample contamination, sample handling problems, or assay interference can skew sodium, chloride, or bicarbonate values and produce a misleading gap. If the value does not match the clinical picture, repeat testing and assess whether the specimen may have been compromised.
A second issue is ignoring hyperalbuminemia or assuming albumin is always low in ICU patients. Although hypoalbuminemia is far more common, unusually high albumin can increase the measured gap. This is less frequent but still relevant when there is dehydration or hemoconcentration.
Unmeasured cations can also affect interpretation. Lithium, marked hypermagnesemia, and severe hypercalcemia may reduce the gap by offsetting unmeasured anions. That is, the anion gap is affected by more than just acid production. It is a balance of charges, so the presence of unusual cations can change the expected result.
Additional pitfalls include overreliance on a single value, failure to account for albumin, and ignoring the effect of IV fluids on chloride. An anion gap calculator is helpful, but it should never replace bedside reasoning. The most accurate interpretation comes from combining the number with the patient’s hemodynamics, medications, renal function, and serial labs.
What do you do after identifying an abnormal anion gap?
When an abnormal gap is detected, the next step is to identify the likely cause and assess severity. Start with initial tests: check lactate, ketones, and a blood gas. These tests are useful for distinguishing lactic acidosis, ketoacidosis, and other major drivers of metabolic acidosis.
Next use clinical correlation. Ask whether the patient has shock, sepsis, renal dysfunction, toxic ingestion risk, poor intake, diarrhea, or medication exposures. Go through the medication list, urine output, hemodynamics, and recent interventions such as fluid resuscitation or diuretic use.
Apply the progression over time to assess response. Repeated labs can indicate whether the gap is widening, getting better, or holding steady. That trend is often more revealing than the initial measurement because it captures the patient’s evolving physiology and the effect of treatment.
If the gap is high, address the underlying problem while verifying the diagnosis. If the gap is normal but acidosis persists, consider normal anion gap causes such as diarrhea, renal tubular acidosis, or hyperchloremic states. If the gap is unexpectedly low, recheck albumin and think about unmeasured cations or artifact.
In ICU care, the anion gap is a clinical tool, not a final diagnosis. It helps narrow the differential, steer further testing, and sequence treatment, but it always needs to be integrated with the broader clinical picture.
Frequently asked questions about anion gap interpretation
How does an anion gap calculator help in ICU interpretation?
An anion gap calculator simplifies the initial calculation from sodium, chloride, and MUDPILES mnemonic bicarbonate and minimizes arithmetic errors during busy ICU workflows. It is most helpful as a starting point for interpretation, especially when you are reviewing an acid-base disorder in real time. The calculator does not replace clinical judgment, albumin adjustment, or follow-up testing.
Why is the anion gap lower in hypoalbuminemia?
Hypoalbuminemia decreases the gap because albumin is a major unmeasured anion. When serum albumin drops, fewer negative charges are present in the blood, so the measured anion gap falls even if an acid load is present. That is why the albumin-corrected anion gap is often used in critically ill patients.
What is the difference between high and normal anion gap metabolic acidosis?
High anion gap metabolic acidosis reflects accumulation of unmeasured acids such as lactate, ketones, or toxins. Normal anion gap metabolic acidosis usually results from bicarbonate loss or chloride gain, such as with diarrhea or renal tubular acidosis, and is often associated with hyperchloremia. The distinction matters because it clarifies the diagnostic approach and points to different causes.
When do you calculate an albumin-corrected anion gap?
You should calculate an albumin-corrected anion gap whenever albumin is reduced or suspected to be low, which is common in critical illness. It is particularly helpful when the measured gap seems normal but the patient appears to have metabolic acidosis or another concerning acid-base disorder. Correction helps reveal hidden high-gap states.
Can serious metabolic acidosis still happen with serious metabolic acidosis?
Yes. A patient can have serious metabolic acidosis with a normal anion gap, particularly in diarrhea, renal tubular acidosis, or chloride-rich fluid states. A normal gap does not eliminate clinically important acid-base disease, so the full evaluation should include pH, bicarbonate, chloride, albumin, lactate, ketones, and the overall ICU context.