What the Anion Gap Measures
The anion gap is a practical way to look at the balance of charged particles in the blood, especially when evaluating serum electrolytes and overall acid-base balance. It is not a direct value of a single substance. Instead, it is a calculated estimate that reveals the difference between commonly measured positive ions and negative ions in a standard chemistry panel.
An anion gap calculator uses routine lab values to estimate how many unmeasured anions may be present in the bloodstream. This makes it a practical diagnostic aid in the normal AG metabolic acidosis management assessment of acid-base disorders, especially metabolic acidosis. In plain terms, if the gap is increased or reduced than expected, it can point to underlying changes in the body’s chemical balance.
The calculation is part of everyday serum chemistry and is commonly derived from an electrolyte panel. It is especially useful because the result can suggest whether an acid load is present, whether there may be changes in renal function, or whether additional testing is needed to clarify the cause of an abnormal result. The anion gap is best understood as a guide, not a final diagnosis.
How to Compute the Anion Gap from Lab Results
The classic anion gap formula includes three lab values: sodium, chloride, and bicarbonate. In most cases, the calculation is:
Anion gap = sodium - (chloride + bicarbonate)
This formula compares the dominant measured cation, sodium, against the major measured anions, chloride and bicarbonate. The result indicates the amount of unmeasured anions in the blood. Because different laboratories may report slightly different values or use different methods, the exact interpretation should always be tied to the lab’s own reference interval.
To work with an anion gap calculator correctly, enter the values from the same blood draw. Mixing results from different times can distort the clinical interpretation. Also check whether the calculator is using the traditional formula or a version that includes potassium, since that changes the number slightly. Most routine clinical use focuses on the sodium-based version.
As an example: if sodium is 140, chloride is 104, and bicarbonate is 24, the calculation is 140 - (104 + 24) = 12. That result is often considered within a typical range, but the exact normal anion gap depends on the lab method and the reporting system.
Anion Gap Calculator Inputs and Outputs
An reliable anion gap calculator is only as reliable as the lab values provided into it. The key inputs are sodium, chloride, and bicarbonate, and the output is the calculated result. Some calculators also display the expected reference range so the user can quickly see whether the result is low, normal, or high.
Understanding the output requires more than just comparing a number to a cutoff. A good calculator should help connect the result to the broader laboratory analysis. For example, a result somewhat above the reference range may be meaningful in the context of symptoms or other abnormal chemistry findings, while a greater elevation can suggest a more significant disorder in acid-base status.
Some calculators include albumin adjustment, which is useful because a low albumin can decrease the measured gap. This is one reason the raw result should be treated as a corrected value only after assessing the patient’s protein status and other findings. Using the calculator wisely helps improve clinical interpretation and reduce common mistakes.
Standard Anion Gap vs High Anion Gap
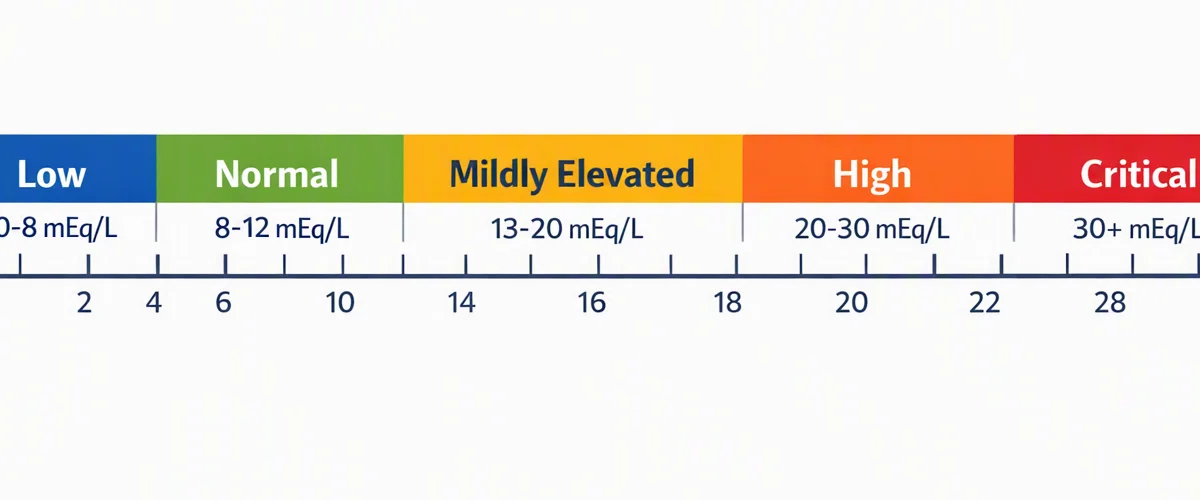
The normal range for the anion gap differs by lab, assay method, and whether potassium is part of the calculation. In most cases, a typical anion gap indicates that the balance between measured cations and anions is preserved, while a increased anion gap implies extra unmeasured acids or anions are present.
A increased anion gap is especially relevant in the evaluation of metabolic acid buildup. In this situation, bicarbonate is often consumed as the body cushions excess acid, and the calculated gap rises as new unmeasured substances accumulate in the blood. This pattern points toward a form of acid-base abnormalities that usually needs further workup rather than simple observation.
A normal result does not always mean there is no problem. Some types of metabolic acidosis occur with a normal gap, particularly when bicarbonate is lost and chloride rises to replace it. That is why the anion gap should be used as one part of a broader serum chemistry review, not in isolation.
Typical Causes for High Anion Gap
A number of conditions can cause a high anion gap, and this pattern often reflects build-up of acids or other unmeasured substances. The most common are lactic acidosis, ketoacidosis, renal failure, and contact with certain toxins.
Lactic acidosis occurs when lactate builds up due to poor oxygen delivery, shock, severe infection, seizures, or other stress states. A rising lactate level may correlate with a higher anion gap, although the two do not always move perfectly together. This makes the anion gap a helpful indicator, but not a stand-in for direct testing.
Ketoacidosis occurs when ketone bodies rise, often in diabetes, prolonged fasting, or heavy alcohol use. In this setting, the body creates an acid load that raises the gap. The result is commonly paired with low bicarbonate and a low pH on blood gas testing.
Renal failure can also cause a high gap because the kidneys are less able to clear acids and keep electrolyte balance. As renal function declines, retained acids gather and contribute to metabolic acidosis. This is one reason the anion gap is frequently considered alongside kidney markers and overall chemistry findings.
Another critical category is toxin exposure. Toxic alcohols such as methanol or ethylene glycol can increase the gap significantly. Salicylates can also trigger complex acid-base changes and should be considered when the history suggests exposure or overdose. In these cases, the anion gap may be an early clue of serious poisoning.
Frequent Causes of a Low Anion Gap
A decreased anion gap is rarer than a high one, but it can still matter clinically. A leading cause is low albumin, since albumin is a negatively charged blood protein that accounts for much of the normal gap. When albumin falls, the measured gap may drop even if no new disorder is present.
Abnormal protein excess is also an important cause. Some abnormal proteins, such as monoclonal immunoglobulins, can alter the charge balance in blood and reduce the apparent gap. This is why an unexpectedly low value may prompt a more careful review of the full chemistry profile and associated clinical picture.
Lab error should also be considered. Minor problems with specimen handling, measurement method, or reporting can create misleading results. If the number does not fit the patient’s condition or changes abruptly without explanation, repeating the test is often the first practical step. In many cases, a low result is less about a dangerous disorder and more about a clue that the numbers need to be verified.
How Serum Albumin Affects an Anion Gap
Albumin serves as one of the main unmeasured negative ions in the blood, so shifts in its level can significantly affect the anion gap. When albumin is decreased, the gap may appear falsely reduced. This is why the corrected anion gap is often used in people with low albumin, especially when assessing metabolic acidosis or other acid-base disorders.
The process of albumin correction raises the result upward to account for missing negative charge from low protein levels. This creates a more accurate corrected value and improves the usefulness of the test as a diagnostic aid. Without correction, a clinically important high gap can be missed if hypoalbuminemia is present.
Because albumin is a major circulating protein, any condition that depletes it can change the apparent balance of electrolytes. This means the raw number and the corrected number may suggest different stories. A thoughtful interpretation should always consider the patient’s protein status, overall acid-base status, and the broader laboratory context.
Using the Anion Gap alongside Other Lab Findings
The anion gap becomes much more informative when reviewed with a blood gas, especially the pH and adjacent markers such as base excess. Together, these results can confirm whether the body is acidemic, alkalemic, or compensating for a mixed disorder. This combined view improves clinical interpretation and gives a more complete picture of acid-base status.
For example, a high anion gap with low pH and low bicarbonate strongly supports metabolic acidosis. If the blood gas shows an unexpectedly normal pH, there can be compensation or a mixed disorder masking the main process. The value of the anion gap is that it helps identify whether excess acids are present even before the pH fully reflects the problem.
Base excess adds another layer of information by estimating the amount of base needed to return blood to normal pH. When paired with the anion gap, it can help distinguish between acute and chronic processes and clarify whether the body is dealing with an acid load. Reviewing all of these numbers together is far more informative than relying on a single value.
If to Seek Medical Interpretation
An abnormal anion gap should be reviewed with a clinician when it is associated with symptoms, severe illness, or other abnormal lab findings. The result is most useful when interpreted in context, especially if there are signs of dehydration, confusion, shortness of breath, vomiting, abdominal pain, or altered mental status. These symptoms may signal a serious acid-base problem.
Clinician review is especially important when the value is markedly high or low, when there are critical values on the chemistry panel, or when the pattern suggests toxin exposure, severe renal function impairment, or an uncontrolled metabolic disorder. A calculator can support decision-making, but it cannot replace medical judgment or a full history and exam.
It is prudent to seek interpretation if the result fails to match the overall picture, because lab error, collection problems, or missed albumin shifts can alter the outcome. The most effective approach is to use the anion gap as part of a more complete review of the patient’s condition, not as a single diagnosis.
FAQs
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the anion gap from routine lab results, usually sodium, chloride, and bicarbonate. It helps with interpretation of electrolyte changes, especially when evaluating metabolic acidosis and other acid-base disorders. It is a useful tool for reviewing serum electrolytes and identifying possible unmeasured acids.
How do you calculate anion gap from lab results?
The usual anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium - (chloride + bicarbonate). Enter the values from the same sample into the anion gap calculator to obtain the result. Always compare the number to the lab’s reference range, since the expected interval can differ by method and reporting system.
What does a high anion gap mean?
A high anion gap often means there are extra unmeasured anions in the blood, usually from an acid buildup. Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylates. It is a useful clue in the evaluation of metabolic acidosis, but it should be interpreted with blood gas findings and the clinical picture.
Can a low albumin level change the anion gap?
Yes. Hypoalbuminemia can lower the measured gap because albumin is an important negatively charged protein. In that situation, a corrected anion gap may be more reliable than the raw number. This albumin correction helps avoid missing a medically significant acid-base problem.
What should I do if my anion gap is abnormal?
If your anion gap is abnormal, the following step is usually provider review of the complete set of lab values, signs, and related tests such as a blood gas. The interpretation depends on whether the result is high, low, or affected by testing error, albumin changes, or another condition. Seek prompt medical attention if you have concerning signs or if the result is marked as a critical value.