What is hyperchloremic metabolic acidosis?
Hyperchloremic metabolic acidosis is a type of metabolic acidosis in which the body’s pH balance shifts toward greater acidity because bicarbonate is reduced, and chloride rises to maintain electrical neutrality. This pattern is also known as normal anion gap metabolic acidosis or normal gap acidosis because the anion gap usually stays within the expected range.
To understand the condition, it helps to think of the bloodstream as a tightly regulated system of charged particles. The main measured ions include sodium, chloride, and potassium, along with bicarbonate and other less measurable ions. When bicarbonate falls, the body often keeps more chloride, producing chloride elevation. This is why the disorder is called hyperchloremic metabolic acidosis.
The key issue is not simply “too much acid” in the abstract. The problem is usually either bicarbonate loss from the gastrointestinal tract or kidneys, or impaired renal acidification. In both cases, acid-base status becomes abnormal, and the serum chemistry pattern shifts in a distinct way.
In clinical practice, this is an acid-base disorder that clinicians often suspect from basic laboratory values before confirming it with more detailed testing. Because the anion gap often stays normal, identifying the condition depends on careful lab interpretation rather than just looking for a high-gap pattern.
How may an anion gap calculator work?
An anion gap calculator assists determine whether the measured electrolytes fit a normal anion gap or high-gap acid-base pattern. It typically uses serum sodium, serum chloride, and serum bicarbonate measurements from a blood test. The calculation is used during the diagnostic workup to evaluate whether the patient’s metabolic acidosis is consistent with hyperchloremic metabolic acidosis or a different disorder.
The basic idea is straightforward: when you compare sodium with the sum of chloride and bicarbonate, you can infer the gap created by unmeasured ions. A normal or near-normal result suggests normal anion gap metabolic acidosis, while a widened gap suggests other causes. This is why the anion gap calculator is so helpful for separating one type of acid-base disorder from another.
In hyperchloremic metabolic acidosis, the drop in bicarbonate is usually matched by a rise in chloride, so the gap does not increase much. That https://anion-gap-tracker310.nexorafield.com/posts/how-the-anion-gap-helps-diagnose-acid-base-imbalances pattern helps distinguish it from lactic acidosis or ketoacidosis, where the anion gap is usually elevated because of accumulated acid anions.
A calculator does not replace clinical judgment, but it complements blood gas analysis and broader laboratory interpretation. It is especially helpful when paired with a serum chemistry panel, serum electrolytes, and an arterial blood gas. Together, these tests show whether the low bicarbonate reflects metabolic acidosis and whether respiratory metabolic compensation is under way.
Important details to review include:
- Sodium level, which forms the basis of the calculation Chloride level, which often goes up in this condition Bicarbonate level, which is usually low Potassium, which may be low, normal, or high depending on the cause
In short, the anion gap calculator helps evaluate whether the pattern fits a normal gap acidosis and directs the clinician toward the next step in evaluating the underlying etiology.
What causes hyperchloremic metabolic acidosis?
A number of conditions can lead to hyperchloremic metabolic acidosis, but the main causes usually involve either gastrointestinal loss of bicarbonate or decreased kidney ability to handle acid and bicarbonate. The major causes include diarrhea, renal tubular acidosis, saline infusion, and kidney disease.
Diarrhea is a classic cause because the intestines can lose large amounts of bicarbonate-rich fluid. This creates bicarbonate loss and a secondary rise in chloride. In this setting, dehydration may also be present, making the acid-base problem worse. The clinical picture may include volume depletion, weakness, and abnormal electrolyte levels.
Renal tubular acidosis occurs when the kidneys cannot properly excrete acid or reclaim bicarbonate. This disorder is a leading cause of persistent normal gap acidosis and often requires a focused evaluation of renal function, urine studies, and the broader acid-base disorder. Because the kidneys are central to renal acidification, any defect in that process can lower serum bicarbonate and disturb acid-base balance.
Saline infusion can also cause hyperchloremic metabolic acidosis, especially after substantial amounts of chloride-rich intravenous fluids. In this case, the problem is not acid overproduction but a dilutional and compositional shift in the serum. The chloride load increases while bicarbonate falls, leading to a transient non-gap acidosis. This is one reason clinicians watch fluid choice carefully when giving intravenous fluids.
Kidney disease can contribute by limiting the ability to excrete acid and maintain normal bicarbonate levels. Depending on the stage and type of renal dysfunction, the patient may have mixed features, but chronic renal impairment can certainly produce a hyperchloremic pattern, especially early on before other retained acids accumulate.
Various contributing factors may involve the effects of medications, tubule defects, and disorders that cause persistent bicarbonate losses. The common thread is that the body either is depleted of bicarbonate, receives too much chloride, or cannot effectively preserve compensatory metabolism.
What are the signs and lab findings?
The manifestations of hyperchloremic metabolic acidosis depend on the severity and the primary cause. Some people have slight or general clinical symptoms, while others present with clear signs of acid-base disturbance. Common complaints include fatigue, weakness, decreased ability to exercise, and sometimes dyspnea from compensatory breathing.
Tachypnea, or increased respiratory rate, can occur as the body tries to reduce carbon dioxide and help compensate for the acid-base disturbance. This respiratory response is part of the body’s metabolic compensation. If the acidosis is more severe, breathing may become more deep and more rapid as well.
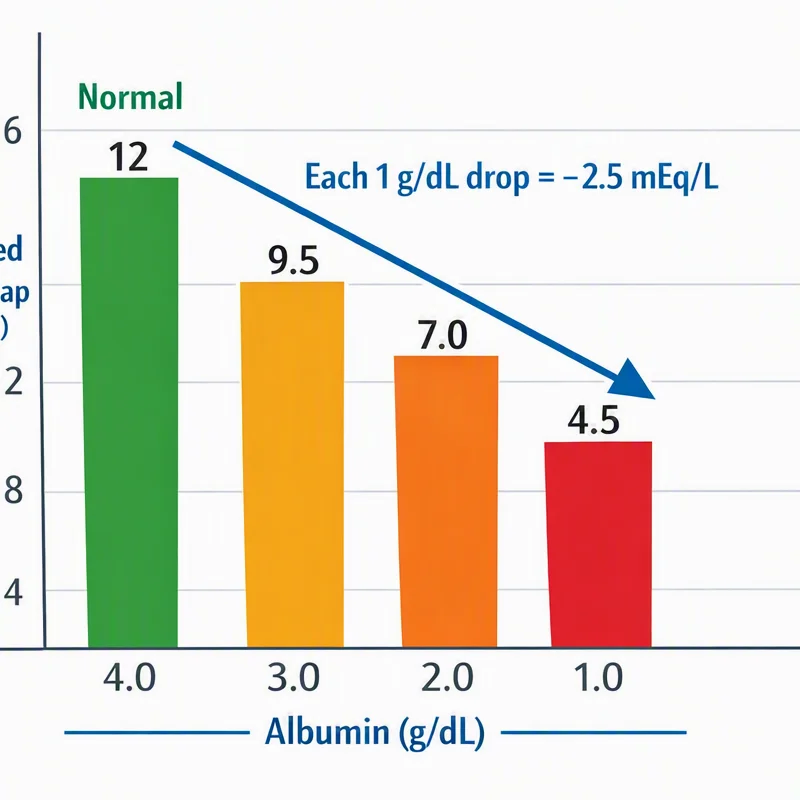
Lab findings usually start from a serum chemistry panel showing low bicarbonate and elevated chloride. A full blood chemistry panel or serum electrolytes test can also reveal abnormalities in sodium and potassium, depending on the cause. Potassium changes are especially important because acid-base disorders and renal problems often affect electrolyte levels at the same time.
An arterial blood gas helps confirm the diagnosis by showing low blood pH if the acidosis is not fully compensated. It also shows whether the respiratory system is reacting properly. In many cases, the blood gas and chemistry panel work together: the chemistry panel identifies a low serum bicarbonate, while the arterial blood gas clarifies the blood pH and respiratory compensation.
Typical laboratory clues include:
- Low serum bicarbonate Normal or near-normal anion gap High chloride Possible shifts in potassium Abnormal blood pH on arterial blood gas
The overall pattern assists in separating this disorder from other acid-base disorders. The lab picture is especially important because the symptoms can be general and overlap with dehydration, infection, kidney dysfunction, or other causes of malaise.
How is it handled and managed?
Treatment depends on the underlying cause and the extent of the acid-base disturbance. The first goal is usually to fix the source of bicarbonate loss or chloride excess and then restore a stable electrolyte imbalance. For some patients, treatment is straightforward and supportive; for others, especially those with kidney disease or renal tubular acidosis, management may be ongoing.
Fluid replacement is often needed when diarrhea or dehydration has contributed to the acidosis. Rehydration improves circulation, supports kidney function, and helps restore acid-base balance. If the acidosis developed after large amounts of chloride-rich fluids, clinicians may modify the type of intravenous fluids and monitor labs closely.
Bicarbonate therapy may be used in selected cases when the bicarbonate level is very low or symptoms are more severe. This treatment should be individualized because too much bicarbonate can create complications, and the decision depends on the clinical picture, blood pH, kidney function, and the rate of ongoing losses. In many situations, correcting the cause is more important than replacing bicarbonate alone.
When renal tubular acidosis is present, treatment may include alkali supplementation and management of any potassium abnormality. If kidney disease is the driver, care focuses on the broader renal condition and maintaining stable electrolyte levels. If diarrhea is the cause, treatment targets the gastrointestinal problem, fluid losses, and any associated dehydration.
Management often includes:
- Addressing the underlying cause Treating dehydration with fluid replacement Checking and treating electrolyte imbalance Starting bicarbonate therapy when appropriate Rechecking lab tests to follow serum bicarbonate and blood pH
Ongoing follow-up matters because recurrence is possible if the cause is chronic. The goal is to normalize the acid-base state while preventing complications from both acidosis and overcorrection.
How is it different from other metabolic acidoses?
Hyperchloremic metabolic acidosis stands apart from other forms of metabolic acidosis mainly by its anion gap behavior. In this disorder, the gap is usually unchanged because the loss of bicarbonate is matched by a rise in chloride. That is why it is also called normal anion gap acidosis or normal anion gap metabolic acidosis.
In comparison, high anion gap metabolic acidosis occurs when circulating acids accumulate in the blood. Common examples include lactic acidosis and ketoacidosis. In those conditions, bicarbonate falls, but chloride does not rise enough to keep the gap normal. As a result, the anion gap increases and points the clinician toward a separate diagnosis.
This difference is clinically important because the causes, workup, and treatment can change substantially. For example, lactic acidosis may reflect poor tissue oxygen delivery, severe infection, or shock, while ketoacidosis often occurs with insulin deficiency or starvation states. Those problems require urgent condition-specific treatment, not just bicarbonate replacement.
Hyperchloremic metabolic acidosis is often more directly tied to bicarbonate loss, chloride gain, or impaired renal handling of acid. That is why clinicians use the anion gap calculator early in the evaluation: it focuses the diagnosis and improves the efficiency of the diagnostic workup.
In everyday terms:
- Normal anion gap metabolic acidosis points to bicarbonate loss or chloride retention High anion gap metabolic acidosis indicates accumulation of acids like lactate or ketones Lactic acidosis and ketoacidosis usually produce a increased gap
That distinction helps clinicians read labs correctly and choose the right next steps.
When should you request medical evaluation?
You should request medical evaluation if symptoms suggest significant acid-base disturbance, especially when dehydration, ongoing diarrhea, rapid breathing, or confusion are present. While mild cases may be hard to notice, severe acidosis can become dangerous and may require prompt assessment of blood pH, kidney function, and electrolyte balance.
Medical assessment is important because symptoms alone cannot establish the diagnosis. A clinician may examine the history, physical exam, and labs to decide whether the problem is due to diarrhea, renal tubular acidosis, kidney disease, saline infusion, or another cause. That broader clinical assessment is essential for finding the source and determining whether urgent treatment is needed.
Seek evaluation without delay if you have:
- Severe or severe diarrhea Signs of dehydration such as dizziness or low urine output Confusion, severe weakness, or worsening fatigue Fast breathing or tachypnea Known kidney problems or suspected kidney disease
If a clinician suspects metabolic acidosis, the next steps often include an arterial blood gas, a serum chemistry panel, and a review of serum electrolytes. These tests help determine whether the blood pH is low, whether bicarbonate is reduced, and whether the condition is hyperchloremic metabolic acidosis or another acid-base disorder.
Prompt evaluation matters because the underlying cause may require immediate treatment, especially if there is significant dehydration, severe electrolyte imbalance, or changing mental status.
Frequently asked questions
What does the term hyperchloremic metabolic acidosis mean?
Hyperchloremic metabolic acidosis means the blood has become acidic because bicarbonate is low, and chloride has risen to replace it. It is a anion gap clinical significance form of metabolic acidosis with a normal anion gap, so the anion gap usually does not increase much. The pattern is often linked to diarrhea, renal tubular acidosis, saline infusion, or kidney disease.
How does anion gap calculator help diagnose it?
An anion gap calculator helps determine whether the acid-base disorder is probably a normal-gap metabolic acidosis or a high anion gap disorder. By using sodium, chloride, and bicarbonate values from the lab, it helps doctors analyze the serum chemistry panel and decide whether the pattern fits hyperchloremic metabolic acidosis, lactic acid buildup, ketoacidosis, or another cause. It is a valuable tool in diagnosis, but it should be interpreted with clinical judgment and blood gas analysis.
Which are the most common causes of hyperchloremic metabolic acidosis?
The primary reasons are intestinal fluid loss, tubular kidney acidosis, normal saline administration, and kidney disease. These causes either result in bicarbonate loss, decrease renal acidification, or raise chloride to a degree to produce a normal gap acidosis. The underlying etiology dictates the best treatment strategy.
What tests are used to confirm the condition?
Typical lab studies often include a serum chemistry panel, serum electrolytes, and an arterial blood gas. These analyses reveal bicarbonate, chloride, sodium, potassium, blood pH, and the overall acid-base status. Providers may also use the anion gap calculator to aid in laboratory interpretation and differentiate this disorder from high anion gap metabolic acidosis.
How is hyperchloremic metabolic acidosis managed?
Therapy focuses on the underlying reason, along with replacement of fluids and management of electrolyte abnormality. Alkali therapy may be considered in selected cases, especially when bicarbonate is extremely low or symptoms are more severe. If diarrhea, dehydration, kidney disease, or renal tubular acidosis is present, care addresses that specific problem to restore acid-base stability and reduce recurrence.