An Anion Gap Calculator may help you interpret a routine blood test by revealing whether your result falls within the expected typical anion gap range. The anion gap is a valuable clue about fluid and electrolyte balance and acid-base status, especially when a clinician is searching for hidden causes of illness. It is not a diagnosis by itself, but it is a important diagnostic indicator when interpreted with the rest of the blood chemistry.
For adult patients, the normal value depends on the lab, the method used, and whether the result is reported with or without potassium. That is why a calculation tool can be convenient, but the final answer always depends on the lab’s lab range and the full clinical picture.
How anion gap is measured
The anion gap is a computed number that reflects the disparity between the chief positively charged and negatively charged electrolytes in the blood. In simple terms, it approximates the amount of unmeasured anions that are not directly listed on a standard serum chemistry panel or electrolyte panel.
The most common values used in the anion gap formula are sodium, chloride, and bicarbonate. A few formulas also include potassium. Because these are measured ions on a standard blood test, the calculation offers clinicians a quick view of the body’s electrolyte balance and potential acid-related problems.
Why should it be considered? When acids rise or certain substances go up in the blood, the anion gap can change. That makes it a useful screening test for conditions that affect acid-base status. It is especially helpful useful when evaluating a metabolic disorder or signs of acid accumulation.
See it as a gap between what is measured and what is expected. If that gap is wider or lower than normal, it may point to a shift in chemistry that deserves attention.
Typical anion gap range in adults
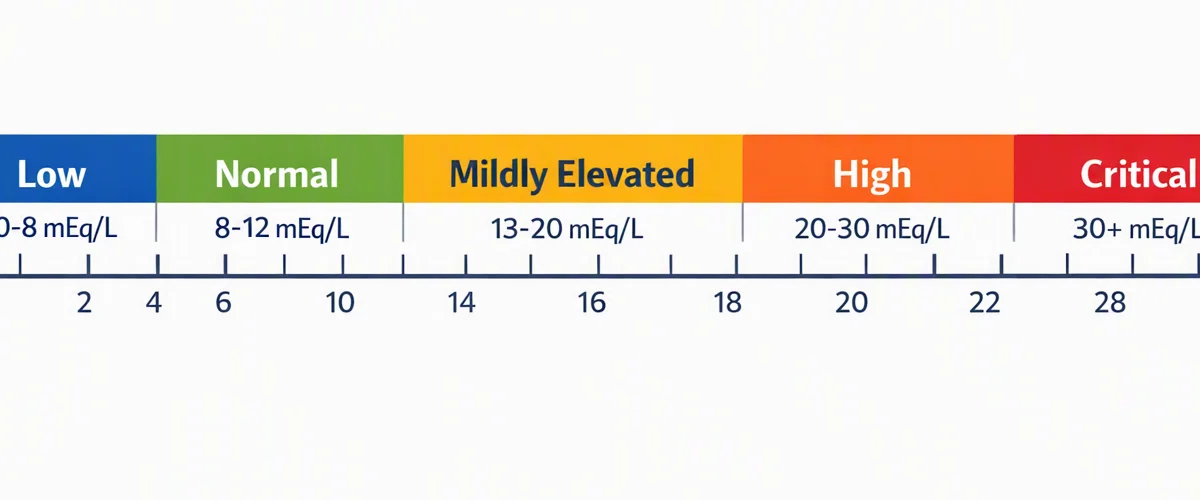
The typical normal range for an adult anion gap is often roughly 8 to 12 mEq/L when potassium is not included, though many laboratories use different numbers. Some lab reports may show a broader reference range, such as about 3 to 11 or 4 to 16 mEq/L, depending on the method and analyzer.
For adults, there is no single standard number. Instead, the accurate interpretation comes from the lab’s own reference interval and the way the result is reported. A value that looks “high” on one report may be inside the expected laboratory values on another.
Because of that, the best approach is to compare the result to the range printed on the report from the specific blood test. A result should be viewed in relation rather than in isolation. The same applies whether the test was part of a serum chemistry panel, a complete blood chemistry workup, or an electrolyte panel.
In practice, clinicians care less about a precise textbook number and more about whether the result aligns with the patient’s symptoms, the rest of the labs, and the suspected diagnosis.
Why the range can change by lab and method
The reported reference range can differ because different labs use different instruments, different testing method settings, and different calibration standards. Small technical differences can move the final result enough to affect the printed reference interval.
Another major factor is albumin. Albumin is a negatively charged protein in the blood, and it helps determine the anion gap. If albumin is low, the gap can appear lower than expected even if the body has another problem. This is one reason an albumin-corrected anion gap can be useful for better clinical interpretation.
Because albumin is one of the main unmeasured anions, a low level may mask a significant acid problem. This is especially important in people with chronic illness, poor nutrition, inflammation, or fluid shifts. In those cases, the lab’s standard range may not tell the full story.
Different analyzers also handle sodium, chloride, and bicarbonate slightly differently. That means the same person could receive a slightly different anion gap from another laboratory. This is normal and AG units clinical significance usually reflects the lab-specific range, not a mistake.
When a clinician sees an unexpected result, they often consider whether the range should be adjusted for albumin and whether the test was performed using a method that tends to run higher or lower than others.
How to work out the anion gap
The usual anion gap formula is straightforward:
Anion gap = sodium - (chloride + bicarbonate)
Certain versions include potassium:
Anion gap = sodium + potassium - (chloride + bicarbonate)
An Anion Gap Calculator works out this math right away. You enter the lab values from the blood test, and the tool produces the calculated gap. This can be especially useful when reviewing a serum chemistry panel or an electrolyte panel and trying to understand whether the number is normal, low, or elevated.
Below is a simple example without potassium:
- Sodium: 140 Chloride: 104 Bicarbonate: 24
The calculation would be 140 - (104 + 24) = 12. That result would often fall within a standard adult reference range, depending on the lab.
Why choose a calculator instead of doing it by hand? A calculator lowers the chance of error, saves time, and helps when comparing several lab sets over time. It also supports better clinical interpretation when the numbers are borderline or when there is concern for an abnormal result.
Some practitioners also consider the serum bicarbonate level separately, because it helps explain whether the body may be dealing with acid loss, acid gain, or compensation. The anion gap does not replace the full acid-base workup; it adds to it.
How a decreased, normal, or raised anion gap may mean
A result within the normal range is often comforting, but it does not rule out illness. A normal value can still occur in a person with a real problem, including normal anion gap metabolic acidosis. On the other hand, a high result may point to an acidic disorder that needs prompt review.
Reduced anion gap
A low anion gap is less common than a high one. One frequent reason is hypoalbuminemia, where albumin is reduced and the gap appears lower than expected. Other causes may include lab variation, certain medications, or uncommon changes in blood proteins. Because albumin strongly affects the calculation, clinicians often think about the albumin-corrected anion gap when the number is unexpectedly low.
Expected anion gap
A normal value generally means the measured electrolytes fit the lab’s expected reference interval. However, a normal result does not always mean everything is fine. Some forms of acidosis, especially normal anion gap metabolic acidosis, can occur when bicarbonate is lost but chloride rises to balance it. In those cases, the total gap may remain normal even though there is a true acid-base problem.
Elevated anion gap
A high anion gap suggests extra acid or unmeasured substances in the blood. Common causes include metabolic acidosis, lactic acidosis, and problems related to kidney disease or kidney failure. When the kidneys cannot clear acids well, the gap may rise. Lactate buildup can also increase the gap during conditions such as poor oxygen delivery, severe infection, or other stress states.
In these situations, the anion gap is a useful clue, but it does not tell the whole story. A clinician may also review renal function, oxygen status, medications, and other labs to find the cause of the acid load.
Because the anion gap can change for several reasons, it should be seen as part of a broader pattern. A single abnormal number may suggest a problem, but the actual diagnosis depends on the rest of the evaluation.
When to seek clinical interpretation
You should ask a doctor to review the result if the anion gap is outside the usual range, if you have worrisome symptoms, or if other values on the blood test are unexpected. Important symptoms include disorientation, breathing quickly, extreme weakness, vomiting, dehydration, or indications of serious illness.
Medical review is especially important if the result suggests an electrolyte imbalance or possible metabolic acidosis. A high value may need prompt assessment, while a low value may require review of albumin, medications, and repeat testing. The interpretation of the number changes depending on the rest of the overall picture.
A doctor may also look for clues across the serum chemistry panel, such as low bicarbonate, abnormal chloride, or changes that point to kidney disease. If there is concern for kidney failure, liver disease, or another metabolic issue, the result may lead to more testing.
It is also wise to seek interpretation when the result is unexpected but you feel well. Sometimes the finding is harmless or due to lab variation. Other times it is an early clue that something needs attention before symptoms become obvious.
Key takeaway: an anion gap result should be interpreted as part of the full blood chemistry, not as a stand-alone diagnosis.
Frequently asked queries
What is the typical anion gap range in adults?
The usual anion gap range in adults is commonly about 8 to 12 mEq/L without potassium, but the precise reference range is determined by the laboratory. Some results use a bit larger or narrower laboratory values, so the lab’s printed reference interval is the clearest guide.
What is considered a high anion gap?
A elevated anion gap is a measurement higher than the lab’s reference range. In numerous cases, values greater than about 12 to 16 mEq/L may be considered abnormal, but the exact cutoff depends on the assay used and whether potassium is included. A high result can suggest metabolic acidosis, lactic acidosis, or another cause of acid accumulation.
Why does albumin affect the anion gap?
Albumin acts as a major unmeasured anion in the blood. With low albumin, the calculated anion gap may appear lower than expected even if there is an underlying acid-base disorder. That is why clinicians may use an albumin-corrected anion gap for more accurate clinical interpretation.
Can the anion gap be normal and still indicate illness?
Absolutely. A typical anion gap does not eliminate illness. As an example, normal anion gap metabolic acidosis can happen when bicarbonate is lost and chloride goes up to compensate. The value may still normal even though there is a genuine metabolic disorder.
How is the anion gap calculated from lab results?
Most often, the anion gap formula is sodium minus chloride plus bicarbonate. Some versions also include potassium. An Anion Gap Calculator can perform this calculation from the serum chemistry test panel or electrolyte report and let you compare the result with the laboratory-specific range.