The anion gap is a derived value that guides clinicians understand a child’s electrolyte balance and overall acid-base balance. When using an Anion Gap Calculator, the main question is usually whether the result falls within the expected normal range for children. In most cases, the answer depends on the laboratory’s reference range, the child’s age, and the rest of the blood test results.
For many pediatric lab tests, a typical anion gap is often considered to be about 8 to 16 mEq/L when albumin is normal, but the exact normal laboratory range can vary by method and institution. Because the result is tied to local laboratory values, it is best read with the child’s serum chemistry panel and overall symptoms in mind.
What’s the Anion Gap?
The anion gap is a numerical approximation of the difference between measured positive and negative charges in the blood. It is not directly measured on its own. Instead, it is derived from electrolytes commonly reported on a serum chemistry panel, especially sodium, chloride, and bicarbonate.
Simply put, the anion gap helps clinicians identify hidden acids in the bloodstream. Because routine lab testing does not measure every charged particle, this calculated value offers useful insight into acid-base disorder patterns. It is especially helpful when trying to identify a metabolic disturbance in a child.
The most common version of the anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some laboratories may apply slightly different formulas or include potassium, so the number can change a little depending on the method. That is why the local reference range matters so much for medical interpretation.
When the value is normal, it generally indicates that the balance between measured cations and anions is expected. When it is abnormal, it can point toward an underlying cause that warrants more evaluation.
Standard Anion Gap Range in Children
The normal range for the anion gap in children is often similar to adults, but the exact normal range depends on the laboratory, the test method, and the child’s age. In numerous settings, a common pediatric range is roughly 8 to 16 mEq/L when potassium is not included. Certain laboratories use a slightly narrower or wider range.
Because children grow and their physiology changes, the child range may differ across age groups, especially in newborns and infants. For that reason, clinicians rely on the lab’s posted reported values rather than a universal number.
A child’s result should also be viewed alongside serum sodium, serum chloride, and serum bicarbonate, since these numbers shape the final calculation. A result that looks mildly abnormal on paper may still be expected in a specific medical context.
Important points to remember:
- The usual range can vary by laboratory. Age may matter, especially in younger children. Albumin levels can affect the result. A single abnormal result is not always clinically significant.
In practice, the anion gap is one piece of the overall assessment. The most useful interpretation comes from combining the number with the child’s symptoms, exam findings, and other blood chemistry results.
How an Anion Gap Calculator Works
An Anion Gap Calculator relies on the anion gap formula to calculate the difference from a child’s lab results. The calculator usually requests sodium, chloride, and bicarbonate, which are part of a standard serum chemistry panel.
This is the basic process:
- Input the child’s serum sodium. Enter the serum chloride. Input the serum bicarbonate. The tool takes away chloride and bicarbonate from sodium. The result is the computed anion gap.
This calculation helps identify whether the child may have an abnormal result related to an acid-base balance issue. If the gap is high, clinicians often evaluate causes of metabolic acidosis. If it is low, they look for issues such as low albumin, hypoalbuminemia, or a possible lab error.
Because the calculator is based on blood chemistry, it reflects the accuracy of the inputs. Small changes in bicarbonate or chloride can alter the final number. That is why a blood test should always be reviewed in context, not in isolation.
The calculator is valuable for quick screening, but it does not replace professional medical interpretation. It is best used as a tool to aid decision-making, not as a stand-alone diagnosis.
What May Cause a High Anion Gap in Children?
A high anion gap usually means there are more acids in the blood that are not being directly measured in the basic chemistry panel. In children, the most common concern is metabolic acidosis. This pattern suggests that the body is producing or retaining acids faster than it can remove them.
Typical causes of a high anion gap include:
- Lactic acidosis, which may develop when tissues are not getting enough oxygen or when the body is under significant stress Ketoacidosis, which may happen during diabetes-related illness or prolonged poor intake Kidney disease or kidney failure, when acid removal is impaired Certain poisonings or toxin exposures, depending on the scenario
Lactic acidosis can appear when a child is very ill, has poor perfusion, or has https://anion-gap-widget025.tearosediner.net/how-to-operate-an-anion-gap-calculator-for-distinguishing-acidosis-types another serious condition affecting metabolism. Ketoacidosis is more common when the body is using fat for fuel instead of glucose, which can happen in diabetes or starvation states. Kidney disease can also lead to a rising gap because the kidneys are less able to clear acid effectively.
A high anion gap is not a diagnosis by itself. It is a clue that supports further evaluation of the child’s symptoms, hydration status, blood sugar, kidney function, and other lab results. This is where diagnostic context matters most.
What Can Lead to a Low Anion Gap in Children?
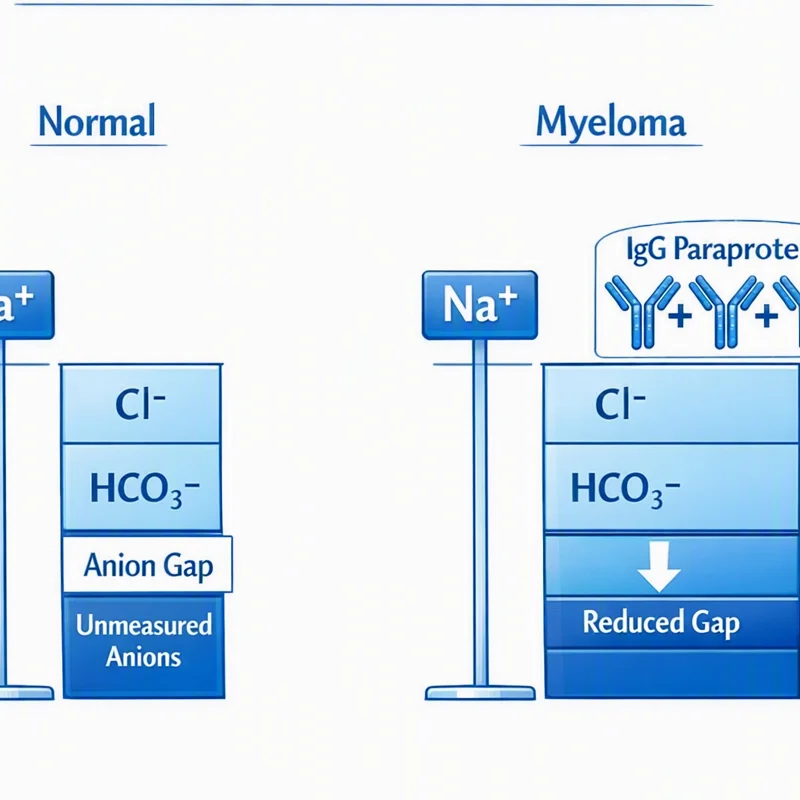
A low anion gap is not as common than a high one, but it can still be important. One of the most frequent explanations is hypoalbuminemia, or low albumin. Albumin is a major negatively charged protein in the blood, so when it drops, the calculated anion gap can fall as well.
Other possible causes of a low anion gap include:
- Lab error or sample handling issues Low albumin from illness, poor nutrition, or protein loss Paraproteins, which are abnormal proteins that can affect the charge balance More rarely, certain medication or measurement effects
When a low value appears, the first step is often to run the test again or review the original specimen for possible lab error. If the result is real, clinicians may check albumin and consider whether hypoalbuminemia explains the finding.
Because low anion gap results can be caused by technical problems, they are often interpreted carefully. A truly low result may still be clinically important, especially if the child has other abnormalities on the blood test or signs of chronic illness. In some cases, paraproteins are part of the explanation, though this is uncommon in pediatrics than in adults.
When Should Parents or Clinicians Be Concerned?
An abnormal anion gap becomes more alarming when it matches the child’s symptoms or other abnormal lab findings. A number outside the expected reference range doesn’t necessarily mean there is an emergency, but it still means the result should be reviewed with the full picture.
Parents and clinicians should pay close attention if the child has dehydration, ongoing vomiting, fast breathing, unusual sleepiness, confusion, poor feeding, or signs of illness that are worsening. These symptoms can point toward a serious metabolic disturbance that needs prompt pediatric evaluation.
Situations that may deserve urgent review include:
- Vomiting with signs of dehydration Difficulty breathing or deep rapid breathing Marked weakness or lethargy Possible diabetic symptoms with concern for ketoacidosis Known kidney disease with worsening lab values
Even without dramatic symptoms, a child with an abnormal result may need follow-up testing if the clinician suspects a developing acid-base problem. The most important question is not simply whether the number is high or low, but whether it corresponds to the child’s overall presentation.
How Doctors Interpret Anion Gap Findings
Doctors interpret an anion gap as part of a full blood test picture. The value helps evaluate acid-base balance, but it is rarely used alone. Instead, the result is compared with the child’s symptoms, exam findings, and other laboratory data.
In many cases, the next step is to examine the full serum chemistry panel and consider whether the child has metabolic acidosis or another acid-base disorder. If the result is high, clinicians may look for lactic acidosis, ketoacidosis, or kidney-related causes. If the result is below normal, they may check albumin and think about hypoalbuminemia or lab error.
An arterial blood gas may be ordered when the diagnosis is unclear or when the child appears seriously ill. This test is used to evaluate acid-base status more directly and can show whether there is a respiratory component or a mixed disturbance. The anion gap then becomes part of a wider medical interpretation.
It is also important to remember that the anion gap is a calculated value, so it can change if sodium, chloride, or bicarbonate shift. Because of that, clinicians often repeat labs or order follow-up testing when the result does not match the expected picture.
Good interpretation always depends on clinical context. A mild abnormality in a well-appearing child may be less concerning than a similar number in a child with dehydration, vomiting, or other warning signs.
Frequently Raised Questions
What is the normal anion gap for children?
The normal anion gap for children is often much like to adults, but the exact normal values depend on the laboratory’s reference range. A common range is about 8 to 16 mEq/L when potassium is not included, but local laboratory values should always guide interpretation.
Does the normal anion gap change with age in children?
Yes, it can. The pediatric normal range may change with age, especially in newborns and infants. Different labs may also use different methods, so age and the testing platform both matter when reviewing pediatric lab tests.
How do you work out the anion gap?
The most common anion gap formula is sodium less the total of chloride and bicarbonate: sodium - (chloride + bicarbonate). An Anion Gap Calculator applies this formula to produce a derived result from the blood chemistry findings.
What can a high anion gap indicate in a child?
A high anion gap usually suggests excess acids in the blood and may indicate acid-base imbalance. Common causes include lactate-related acidosis, ketotic acidosis, and renal impairment. The result should be interpreted with the child’s symptoms and other lab values.
What does a low anion gap mean in a child?
A low anion gap may be caused by hypoalbuminemia, laboratory error, low blood albumin, or sometimes monoclonal proteins. A repeat test or additional evaluation may be needed to confirm whether the result is real and clinically important.
Knowing the anion gap is a useful part of pediatric lab interpretation. When you use an Anion Gap Calculator, the result should always be matched with the child’s symptoms, the full chemistry panel, and the broader clinical context. That approach helps clinicians decide whether the finding is a normal variation or a clue to a more important metabolic issue.